



Angiopeptin
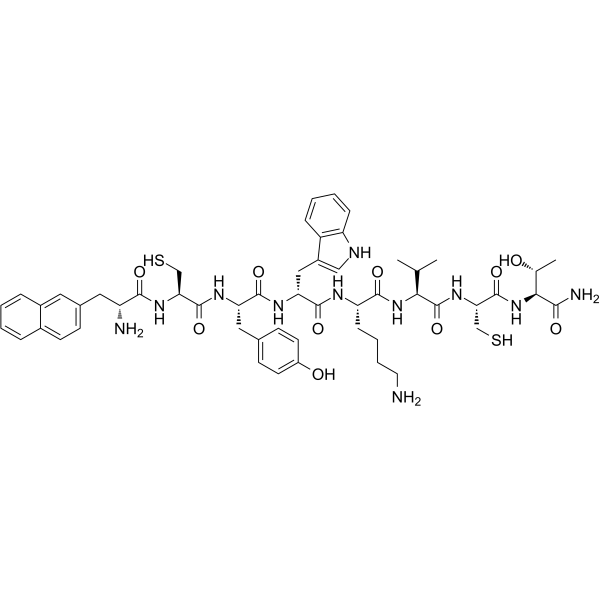
Angiopeptin, a cyclic octapeptide analogue of somatostatin, is a weak sst2/sst5 receptor partial agonist with IC50 values of 0.26 nM and 6.92 nM, respectively. Angiopeptin is a potent inhibitor of growth hormone release and insulin-like growth factor-1 (IGF-1) production. Angiopeptin inhibits adenylate cyclase or stimulates extracellular acidification. Angiopeptin has the potential for coronary atherosclerosis research.
연구목적의 판매만을 진행합니다. 환자를 대상으로 한 판매는 하지 않습니다.
- CAS No.: 113294-82-9
- 화학식: C54H71N11O10S2
- 분자량:1098.34
-
보관:
Please store the product under the recommended conditions in the Certificate of Analysis.

To place orders, for customer services and technical support, please contact: MedChemExpress USA
Tel: 609-228-6898 E-mail: [email protected] [email protected]


-
 Biological Activity
-
Chemical Information
- Protocol
- 순도&문서
- References
-
 Help & FAQs




Biological Activity
제품 설명
IC50 & Target
|
SSTR2 |
SSTR5 |
In Vitro
Angiopeptin (0.1 nM- 10 μM; for 1 h) acts as a partial agonist (pEC50=6.57) with a maximum response of 423% at 3 μM on the release of tritium on CHO hsst2 cells[2].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only. Further protocols information, click here.
In Vivo
Angiopeptin (20 μg/kg; per day) significantly inhibits coronary artery myointimal proliferation in cardiac allografts by appmximalely 50%[1].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only.


Chemical Information
-
CAS No. 113294-82-9
-
분자량 1098.34
-
화학식 C54H71N11O10S2
-
Sequence Shortening
{Nal}CYWKVCT-NH2
-
선적
Room temperature in continental US; may vary elsewhere.
-
보관
Please store the product under the recommended conditions in the Certificate of Analysis.

Protocol
-
Cell Cytotoxicity Assay
Cytotoxicity assays are usually based on the assessment of cell membrane damage, which can also be indirectly detected by measuring cell viability. Detection methods include MTT assay, CKK-8 assay, LDH assay and ATP assay, etc.
-
Research Protocol for Endocrine Diseases
Endocrine diseases often arise from disrupted hormone production, hormone signaling, or target-tissue responsiveness; for diabetes-focused endocrine disease models, insulin signaling regulates glucose uptake, hepatic glucose output, lipid metabolism, and β-cell compensation. Type 2 diabetes develops through interacting defects in insulin resistance, β-cell dysfunction, adipose inflammation, hepatic glucose overproduction, altered incretin signaling, and ectopic lipid metabolism. A major unresolved question is whether endocrine dysfunction is driven primarily by target-tissue insulin resistance, intrinsic β-cell failure, immune/inflammatory stress, or combined multi-organ failure that differs by disease stage.
-
Research Protocol for Cardiovascular Diseases
Cardiovascular disease can be modeled as maladaptive cardiac remodeling, where ischemic injury or pressure overload activates inflammatory signaling, fibroblast activation, extracellular-matrix deposition, cardiomyocyte hypertrophy, vascular remodeling, and progressive ventricular dysfunction. The TGF-β/SMAD axis is a central profibrotic pathway after myocardial injury and pressure overload, while innate immune and cytokine pathways regulate leukocyte recruitment, scar formation, and adverse remodeling. Key unresolved questions include which inflammatory signals are reparative versus harmful, when fibrosis is protective versus maladaptive, and whether pathway inhibition improves function without weakening necessary infarct healing or compensatory remodeling.


순도&문서
References
[1]. Lundergan CF, et al. Peptide inhibition of myointimal proliferation by angiopeptin, a somatostatin analogue. J Am Coll Cardiol. 1991;17(6 Suppl B):132B-136B. [Content Brief]
[2]. Alderton F, et al. Somatostatin receptor-mediated arachidonic acid mobilization: evidence for partial agonism of synthetic peptides. Br J Pharmacol. 2001;132(3):760-766. [Content Brief]

Calculators
Concentration (start) × Volume (start) = Concentration (final) × Volume (final)


Angiopeptin Related Classifications
HY-P2090 Related Classifications
 Powered by Bioz