



FGFR4-IN-6
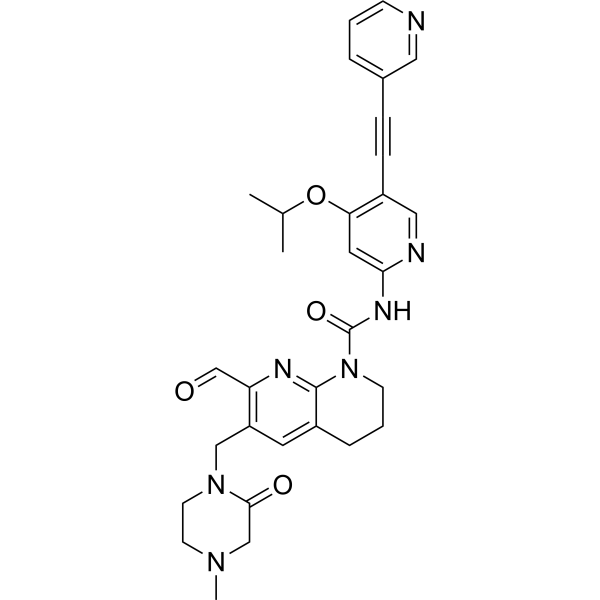
FGFR4-IN-6 (Compound 9ka) is a covalently reversible FGFR4 inhibitor with an IC50 value of 5.4 nM. FGFR4-IN-6 also exhibits good oral pharmacokinetic properties. FGFR4-IN-6 induces significant tumor regressions in a xenograft mouse model of Hep3B2.1-7 HCC cell line without an obvious sign of toxicity. FGFR4-IN-6 is a click chemistry reagent, it contains an Alkyne group and can undergo copper-catalyzed azide-alkyne cycloaddition (CuAAc) with molecules containing Azide groups.
For research use only. We do not sell to patients.
- CAS No.: 2760970-10-1
- Formula: C31H33N7O4
- Molecular Weight:567.64
-
Storage:
Please store the product under the recommended conditions in the Certificate of Analysis.

To place orders, for customer services and technical support, please contact: MedChemExpress USA
Tel: 609-228-6898 E-mail: [email protected] [email protected]


-
 Biological Activity
-
Chemical Information
- Protocols
- Purity & Documentation
- References
-
 Help & FAQs




Biological Activity
Description
Cellular Effect
|
Cell Line

|
Type | Value | Description | References |
|---|---|---|---|---|
| Hep 3B2 | IC50 |
104.13 nM
Compound: 9ka
|
Cytotoxicity against human Hep 3B2.1-7 cells harboring FGF19/FGFR4 assessed as inhibition of cell growth
Cytotoxicity against human Hep 3B2.1-7 cells harboring FGF19/FGFR4 assessed as inhibition of cell growth
|
[PMID: 35119278] |
| Huh-7 | IC50 |
2.4 nM
Compound: 9ka
|
Cytotoxicity against human Huh-7 cells harboring FGF19/FGFR4 assessed as inhibition of cell growth
Cytotoxicity against human Huh-7 cells harboring FGF19/FGFR4 assessed as inhibition of cell growth
|
[PMID: 35119278] |
| MDA-MB-453 | IC50 |
140 nM
Compound: 9ka
|
Cytotoxicity against human MDA-MB-453 cells harboring FGF19/FGFR4 assessed as inhibition of cell growth
Cytotoxicity against human MDA-MB-453 cells harboring FGF19/FGFR4 assessed as inhibition of cell growth
|
[PMID: 35119278] |
| NCI-H1581 | IC50 |
>3 μM
Compound: 9ka
|
Cytotoxicity against human NCI-H1581 cells harboring FGF19/FGFR4 assessed as inhibition of cell growth
Cytotoxicity against human NCI-H1581 cells harboring FGF19/FGFR4 assessed as inhibition of cell growth
|
[PMID: 35119278] |


Chemical Information
-
CAS No. 2760970-10-1
-
Molecular Weight 567.64
-
Formula C31H33N7O4
-
SMILES
O=C(N1CCCC2=CC(CN3C(CN(CC3)C)=O)=C(N=C21)C=O)NC4=CC(OC(C)C)=C(C=N4)C#CC5=CC=CN=C5
-
Shipping
Room temperature in continental US; may vary elsewhere.
-
Storage
Please store the product under the recommended conditions in the Certificate of Analysis.

Protocols
-
EdU Incorporation Assay (Click Chemistry-Based DNA Synthesis Measurement)
The EdU incorporation assay measures DNA synthesis by adding the thymidine analog 5-ethynyl-2′-deoxyuridine to cells or tissues, where it is incorporated into newly synthesized DNA during S phase. Incorporated EdU is detected by copper-catalyzed azide-alkyne cycloaddition, in which a fluorescent azide covalently reacts with the ethynyl group on EdU, allowing S-phase cells to be detected by fluorescence microscopy, flow cytometry, or high-content imaging. EdU detection does not require DNA denaturation or anti-BrdU antibody access, which preserves sample structure and improves compatibility with immunostaining and multiparameter cytometry compared with BrdU-based detection. EdU can be cytotoxic in a cell-type- and exposure-dependent manner, so pulse duration, concentration, and continuous-labeling designs should be validated for each cell type.
-
Cell Cytotoxicity Assay
Cytotoxicity assays are usually based on the assessment of cell membrane damage, which can also be indirectly detected by measuring cell viability. Detection methods include MTT assay, CKK-8 assay, LDH assay and ATP assay, etc.
-
Patient-Derived Xenograft (PDX)
Patient-derived xenograft (PDX) models are generated by engrafting primary human tumor tissue directly into immunodeficient mice, allowing in vivo propagation of patient tumor biology without initial in vitro adaptation. These models are used to preserve key histopathological and molecular characteristics of the original tumor and enable assessment of tumor growth dynamics and therapeutic response in a living organism. The biological readout is tumor engraftment and subsequent growth in the murine host, which reflects the ability of human tumor cells to survive, vascularize, and expand in an immunocompromised microenvironment.
-
Splenic/Portal-Vein Liver Metastasis Xenograft
Splenic and portal-vein liver metastasis xenograft models deliver tumor cells into the portal circulation so that cells reach the liver first and form hepatic metastatic lesions; splenic injection uses the spleen as an access route to the portal system, while direct portal-vein injection introduces cells into the portal vein without requiring splenectomy. The assay detects liver colonization, intrahepatic tumor growth, tumor distribution, treatment response, survival, and liver-metastasis microenvironment changes; readouts include bioluminescence or fluorescence imaging, gross liver nodule counts, liver weight or tumor burden, histology, and survival.
-
Liver Cancer Modeling
Liver cancer can be classified into primary liver cancer and secondary liver cancer. Secondary liver cancer is the metastatic liver cancer. Primary liver cancer includes hepatocellular carcinoma (HCC), intrahepatic cholangiocarcinoma (ICC) and fibrolamellar HCC, of which HCC is the most common form, accounting for approximately 90% of primary liver cancers[1]. HCC mouse models include chemical agent-induced models, transplanted tumor models, and genetic engineered models.
-
Subcutaneous Cell-Line-Derived Xenograft
Subcutaneous cell-line-derived xenograft (CDX) models are established by implanting cultured human cancer cell lines into immunodeficient mice, where the injected cells form localized tumors that can be monitored in vivo as a measure of tumorigenic potential, growth kinetics, and treatment response. These models are widely used in oncology research because they allow reproducible tumor formation and enable comparative assessment of tumor growth between different cell lines or genetic manipulations in a controlled in vivo microenvironment. Subcutaneous implantation of cancer cells in immunodeficient mice is a standard approach for evaluating tumor growth behavior and therapeutic response across multiple cancer types, including prostate, esophageal, pancreatic, and colon cancer models.
-
Orthotopic Cell-Line Xenograft
Orthotopic cell-line xenograft models involve implantation of human cancer cell lines into the anatomically corresponding organ of immunodeficient mice to reproduce tumor growth within a native microenvironment, enabling more clinically relevant tumor behavior compared with subcutaneous models. These models are widely used because orthotopic placement better recapitulates tumor progression, including invasion and metastatic spread, which are often underrepresented in heterotopic implantation systems. Compared with conventional xenografts, orthotopic implantation is described as more technically complex but provides improved simulation of tumor-microenvironment interactions and metastatic behavior, making it particularly valuable for translational oncology research. Surgical orthotopic implantation approaches have been emphasized as enabling faithful reproduction of clinical cancer features, including metastasis and disease progression patterns that align with the tumor’s organ of origi
-
Intraperitoneal/Peritoneal Dissemination Xenograft
Intraperitoneal (IP) or peritoneal dissemination xenograft models are based on the introduction of human cancer cells into the peritoneal cavity of immunodeficient mice, where they attach to peritoneal surfaces, form multicellular aggregates or spheroids, and progressively generate disseminated tumor nodules that mimic advanced peritoneal metastatic disease. These models are widely used to study ovarian cancer progression, tumor-microenvironment interactions, and intraperitoneal therapeutic responses, often incorporating bioluminescence or fluorescence imaging to longitudinally monitor tumor burden in vivo. The biological principle relies on the capacity of tumor cells such as SKOV3 or related ovarian carcinoma lines to survive in suspension, aggregate within ascites-like fluid, adhere to mesothelial surfaces, and invade peritoneal organs, thereby recapitulating human peritoneal carcinomatosis patterns observed in advanced disease.
-
How to Choose the Right Model Animal
Choosing the right model animal is a validity-driven decision in which the species, strain, sex, age, genetic background, disease-induction method, outcome measures, and welfare burden must match the scientific question rather than laboratory tradition or convenience. A model should be selected by judging face validity, construct validity, and predictive validity: whether it resembles the human phenotype, whether it reproduces relevant mechanisms, and whether results are likely to predict human biology or treatment response. Animal studies often fail to translate because of species differences, weak disease resemblance, poor experimental design, inadequate reporting, publication bias, and underuse of randomization, blinding, and sample-size justification. Unresolved questions include how to rank competing models objectively, how much human-disease complexity must be reproduced for a given objective, and when non-animal systems such as organoids, ex vivo tissue, or computational models


Purity & Documentation
References

Calculators
Concentration (start) × Volume (start) = Concentration (final) × Volume (final)


FGFR4-IN-6 Related Classifications
HY-143881 Related Classifications
 Powered by Bioz