



Angiotensin I/II (1-6)
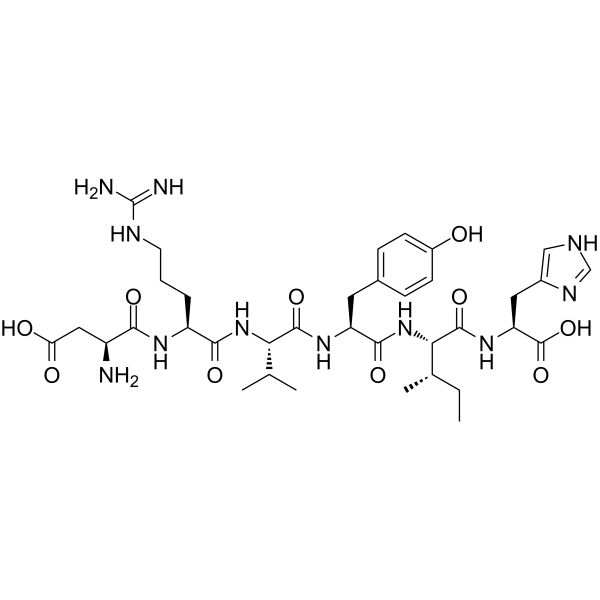
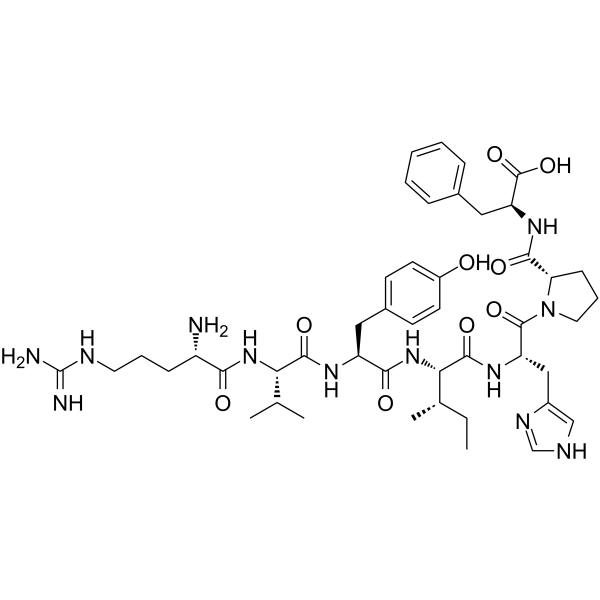
Angiotensin I/II 1-6 contains the amino acids 1-6 and is converted from Angiotensin I/II peptide. The precursor angiotensinogen is cleaved by renin to form angiotensin I. Angiotensin I ishydrolyzed by angiotensin-converting enzyme (ACE) to form the biologically active angiotensin II. Angiotensin II has been investigated for the treatment, basic science, and diagnostic of Hypertension, Renin Angiotensin System, and Idiopathic Membranous Nephropathy.
For research use only. We do not sell to patients.
- CAS No.: 47896-63-9
- Formula: C36H55N11O10
- Molecular Weight:801.89
-
Storage:
Please store the product under the recommended conditions in the Certificate of Analysis.

To place orders, for customer services and technical support, please contact: MedChemExpress USA
Tel: 609-228-6898 E-mail: [email protected] [email protected]


-
 Biological Activity
-
Chemical Information
- Protocols
- Purity & Documentation
- References
-
 Help & FAQs


-
HY-P1032
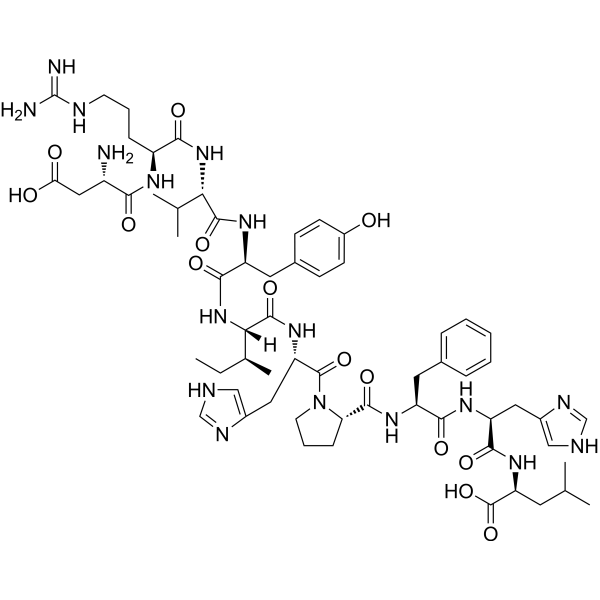
Angiotensin I (human, mouse, rat)Decapeptide Hormone -
HY-12403
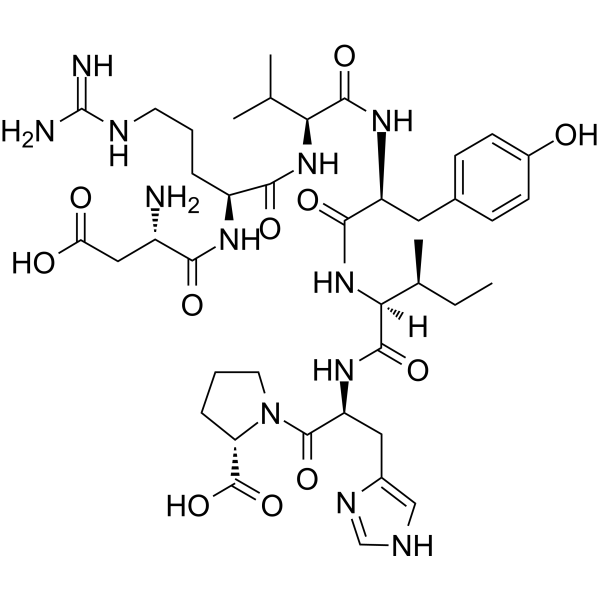
TalfirastideVasodilator Agent -
HY-13948
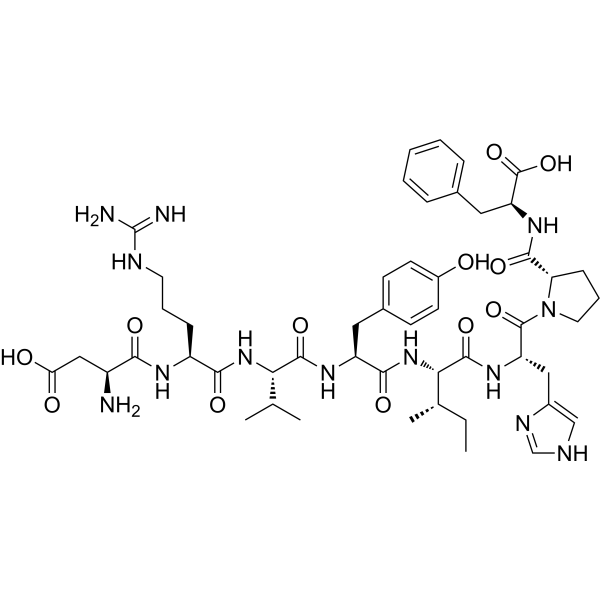
Angiotensin II humanVasoconstrictor -
HY-P1540
Angiotensin III, human, mouseAT2R Agonist -
HY-17512
LosartanAngiotensin II Receptor Antagonist -
HY-18204
ValsartanAngiotensin II Receptor Antagonist -
HY-P0059
TeriparatideParathyroid Hormone Agonist -
HY-13955
TelmisartanAngiotensin II Type 1 Receptor -
HY-B0202
IrbesartanAT1 Receptor Blocker -
HY-B0205
CandesartanAngiotensin II AT1-Receptor Blocker -
HY-17004
OlmesartanAT1R Antagonist -
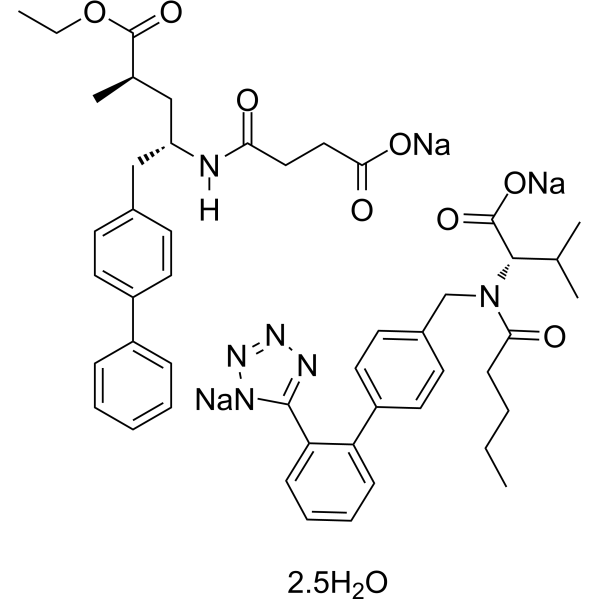
HY-18204A
Sacubitril/ValsartanARN Inhibitor
All Angiotensin Receptor Isoforms
More

Biological Activity
Description
In Vitro
Angiotensin II is a naturally occurring octapeptide hormone component of the renin-angiotensin-aldosterone system (RAAS) and is a potent vasoconstrictor. Angiotensin II has important roles in cardiovascular, neurologic, and renal physiology, including maintenance of blood pressure, thirst sensation, response to the baroreceptor reflex, determination of renal blood flow and glomerular filtration rate, and electrolyte and free water homeostasis[2].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only. Further protocols information, click here.


Chemical Information
-
CAS No. 47896-63-9
-
Molecular Weight 801.89
-
Formula C36H55N11O10
-
Sequence Shortening
DRVYIH
-
Shipping
Room temperature in continental US; may vary elsewhere.
-
Storage
Please store the product under the recommended conditions in the Certificate of Analysis.

Protocols
-
Research Protocol for Cardiovascular Diseases
Cardiovascular disease can be modeled as maladaptive cardiac remodeling, where ischemic injury or pressure overload activates inflammatory signaling, fibroblast activation, extracellular-matrix deposition, cardiomyocyte hypertrophy, vascular remodeling, and progressive ventricular dysfunction. The TGF-β/SMAD axis is a central profibrotic pathway after myocardial injury and pressure overload, while innate immune and cytokine pathways regulate leukocyte recruitment, scar formation, and adverse remodeling. Key unresolved questions include which inflammatory signals are reparative versus harmful, when fibrosis is protective versus maladaptive, and whether pathway inhibition improves function without weakening necessary infarct healing or compensatory remodeling.


Purity & Documentation
References
[1]. Erdös EG, et al. Conversion of angiotensin I to angiotensin II. Am J Med. 1976 May 31;60(6):749-59. [Content Brief]
[2]. Busse LW, et al. Clinical Experience With IV Angiotensin II Administration: A Systematic Review of Safety. Crit Care Med. 2017;45(8):1285-1294. [Content Brief]
[3]. Angiotensin II

Calculators
Concentration (start) × Volume (start) = Concentration (final) × Volume (final)


Angiotensin I/II (1-6) Related Classifications
HY-P1829 Related Classifications
 Powered by Bioz