



CADD522 (Standard)
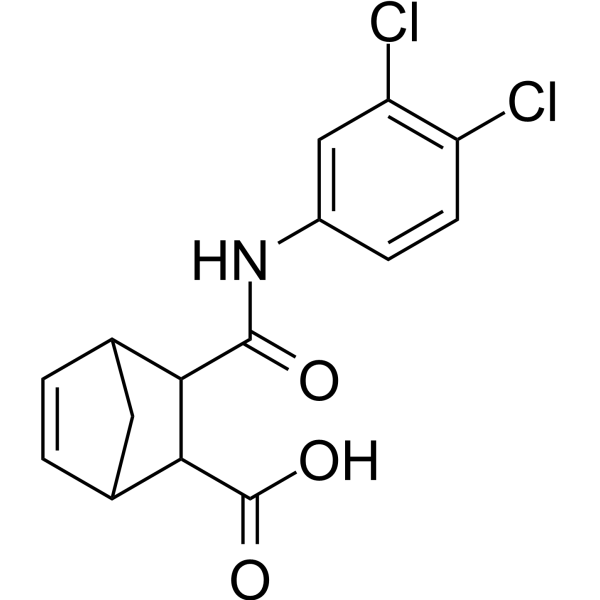
CADD522 (Standard) is the analytical standard of CADD522 (HY-107999). This product is intended for research and analytical applications. CADD522 is a RUNX2-DNA binding inhibitor (downregulates RUNX2-mediated transcription of downstream target genes), with an IC50 of 10 nM. CADD522 inhibits primary tumor growth and experimental metastasis of tumor cells in the lungs of immune-compromised mice. CADD522 can be used in study of cancer.
For research use only. We do not sell to patients.
- CAS No.: 199735-88-1
- Formula: C15H13Cl2NO3
- Molecular Weight:326.17
-
Storage:
Please store the product under the recommended conditions in the Certificate of Analysis.


To place orders, for customer services and technical support, please contact: MedChemExpress USA
Tel: 609-228-6898 E-mail: [email protected] [email protected]


-
 Biological Activity
-
Chemical Information
- Protocols
- Purity & Documentation
- References
-
 Help & FAQs


-
HY-107999
CADD522RUNX2-DNA binding inhibitor -
HY-121026
DMNQRedox cycling Agent -
HY-14937
Succinobucol -
HY-111653
CycLuc1Luciferase Substrate -
HY-13619A
Efaproxiral sodiumHemoglobin Allosteric Modifier -
HY-N9447
NorbergeninAnti-Inflammatory/Antioxidant/Neuroprotective Agent -

HY-14937R
Succinobucol (Standard)Antioxidant -

HY-13619AR
Efaproxiral sodium (Standard)Hemoglobin Allosteric Modifier


Biological Activity
Description
IC50 & Target
RUNX2-DNA binding[1]


Chemical Information
-
CAS No. 199735-88-1
-
Molecular Weight 326.17
-
Formula C15H13Cl2NO3
-
SMILES
ClC1=C(Cl)C=CC(NC(C2C(C3)C=CC3C2C(O)=O)=O)=C1
-
Shipping
Room temperature in continental US; may vary elsewhere.
-
Storage
Please store the product under the recommended conditions in the Certificate of Analysis.

Protocols
-
Protocol for Electrophoretic Mobility Shift Assay (EMSA)
Electrophoretic mobility shift assay detects protein-nucleic acid binding by incubating a labeled DNA or RNA probe with purified protein or cell extract, then separating free probe from slower-migrating protein-probe complexes on a native gel. For cancer cells, primary neurons, mouse tumor samples, intestinal organoids, inflammatory macrophages, or drug-treated samples, EMSA can measure transcription-factor DNA binding or RNA-binding protein activity in extracts, but it does not directly measure transcription, protein expression, or chromatin occupancy in intact cells. Specificity is judged by competition with unlabeled wild-type probe, failure of mutated or unrelated competitors to compete, and antibody supershift or disruption when the binding protein identity must be confirmed.
-
Cell Cytotoxicity Assay
Cytotoxicity assays are usually based on the assessment of cell membrane damage, which can also be indirectly detected by measuring cell viability. Detection methods include MTT assay, CKK-8 assay, LDH assay and ATP assay, etc.
-
Patient-Derived Xenograft (PDX)
Patient-derived xenograft (PDX) models are generated by engrafting primary human tumor tissue directly into immunodeficient mice, allowing in vivo propagation of patient tumor biology without initial in vitro adaptation. These models are used to preserve key histopathological and molecular characteristics of the original tumor and enable assessment of tumor growth dynamics and therapeutic response in a living organism. The biological readout is tumor engraftment and subsequent growth in the murine host, which reflects the ability of human tumor cells to survive, vascularize, and expand in an immunocompromised microenvironment.
-
Tail-Vein Experimental Metastasis Xenograft
Tail-vein experimental metastasis xenograft models assess the ability of injected tumor cells to survive circulation, arrest in vascular beds, extravasate, and colonize distant organs, most commonly lung after lateral tail-vein injection; this model bypasses primary-tumor formation, local invasion, and intravasation, so the readout reflects late metastatic colonization rather than the full metastatic cascade. The main readouts are metastatic burden measured by bioluminescence imaging, gross metastatic nodules, histology, organ weight, survival, or ex vivo tumor-cell quantification; luciferase-labeled tumor cells permit longitudinal noninvasive monitoring, while histology confirms organ colonization and tissue localization.
-
Patient-Derived Orthotopic Xenograft (PDOX)
Patient-derived orthotopic xenograft (PDOX) modeling implants fresh patient tumor tissue or patient-derived tumor cells into the anatomically corresponding organ or tissue site of immunodeficient mice, usually by surgical orthotopic implantation, to preserve patient tumor histology, local microenvironmental context, invasion, metastatic behavior, and treatment-response features better than subcutaneous implantation. PDOX readouts include tumor engraftment, orthotopic tumor growth, local invasion, metastasis, recurrence after resection, histologic similarity to the donor tumor, biomarker retention, molecular concordance, survival, and response or resistance to therapy. PDOX models are used for preclinical drug testing and individualized therapy evaluation, but engraftment success varies by tumor type and specimen quality.
-
Intracardiac/Intra-Arterial Metastasis Xenograft
Intracardiac xenograft metastasis models are based on the direct delivery of fluorescent or bioluminescent tumor cells into the left ventricle of immunocompromised mice, allowing systemic arterial dissemination that mimics hematogenous spread and enables colonization of distant organs such as bone, brain, and lung. Real-time bioluminescence imaging (BLI) is used to non-invasively track tumor cell seeding, survival, and metastatic outgrowth over time, reflecting early arrest in capillary beds followed by organ-specific colonization and proliferation.
-
Subcutaneous Cell-Line-Derived Xenograft
Subcutaneous cell-line-derived xenograft (CDX) models are established by implanting cultured human cancer cell lines into immunodeficient mice, where the injected cells form localized tumors that can be monitored in vivo as a measure of tumorigenic potential, growth kinetics, and treatment response. These models are widely used in oncology research because they allow reproducible tumor formation and enable comparative assessment of tumor growth between different cell lines or genetic manipulations in a controlled in vivo microenvironment. Subcutaneous implantation of cancer cells in immunodeficient mice is a standard approach for evaluating tumor growth behavior and therapeutic response across multiple cancer types, including prostate, esophageal, pancreatic, and colon cancer models.
-
Orthotopic Cell-Line Xenograft
Orthotopic cell-line xenograft models involve implantation of human cancer cell lines into the anatomically corresponding organ of immunodeficient mice to reproduce tumor growth within a native microenvironment, enabling more clinically relevant tumor behavior compared with subcutaneous models. These models are widely used because orthotopic placement better recapitulates tumor progression, including invasion and metastatic spread, which are often underrepresented in heterotopic implantation systems. Compared with conventional xenografts, orthotopic implantation is described as more technically complex but provides improved simulation of tumor-microenvironment interactions and metastatic behavior, making it particularly valuable for translational oncology research. Surgical orthotopic implantation approaches have been emphasized as enabling faithful reproduction of clinical cancer features, including metastasis and disease progression patterns that align with the tumor’s organ of origi


Purity & Documentation
References
[1]. Kim MS, et al. Characterization of CADD522, a small molecule that inhibits RUNX2-DNA binding and exhibits antitumor activity. Oncotarget. 2017 Aug 10;8(41):70916-70940. [Content Brief]
[2]. Kim MS, et al. Targeting breast cancer metabolism with a novel inhibitor of mitochondrial ATP synthesis. Oncotarget. 2020 Oct 27;11(43):3863-3885. [Content Brief]

Calculators
Concentration (start) × Volume (start) = Concentration (final) × Volume (final)


CADD522 (Standard) Related Classifications
HY-107999R Related Classifications
 Powered by Bioz