



L-Thyroxine-13C6
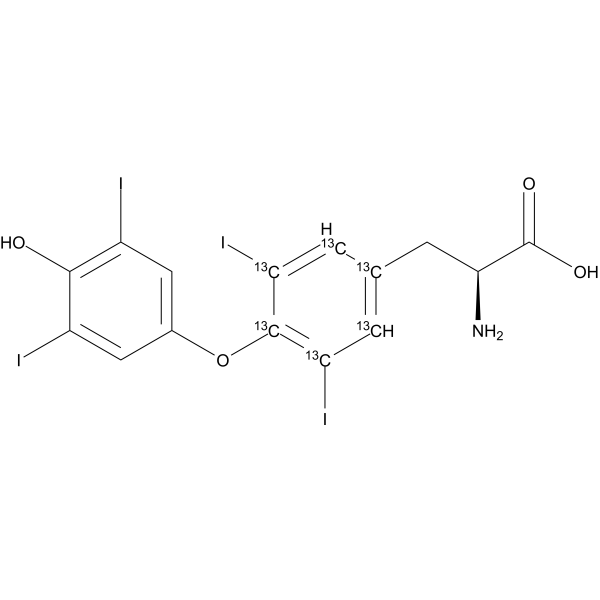
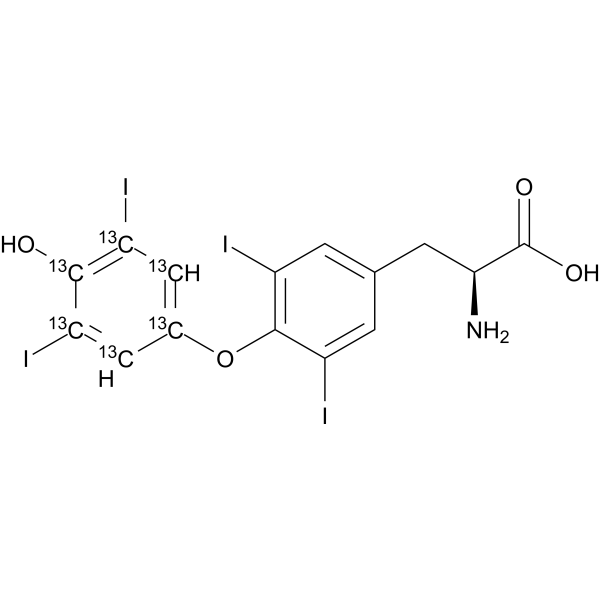
L-Thyroxine-13C6 is the 13C labeled L-Thyroxine. L-Thyroxine (Levothyroxine;T4) is a synthetic hormone for the research of hypothyroidism. DIO enzymes convert biologically active thyroid hormone (Triiodothyronine,T3) from L-Thyroxine (T4).
For research use only. We do not sell to patients.
- CAS No.: 720710-30-5
- Formula: C913C6H11I4NO4
- Molecular Weight:782.83
-
Storage:Powder -20°C, 3 years , 4°C, 2 years ; In solvent -80°C, 6 months , -20°C, 1 month

To place orders, for customer services and technical support, please contact: MedChemExpress USA
Tel: 609-228-6898 E-mail: [email protected] [email protected]


-
 Biological Activity
-
Chemical Information
- Protocols
- Purity & Documentation
- References
-
 Help & FAQs


-
HY-A0070A
LiothyronineTIGIT/PVR Blocker -
HY-A0070AG
Liothyronine (GMP)TRα/TRβ Agonist (GMP) -
HY-A0070AR
Liothyronine (Standard)TRα/TRβ Agonist -
HY-114557
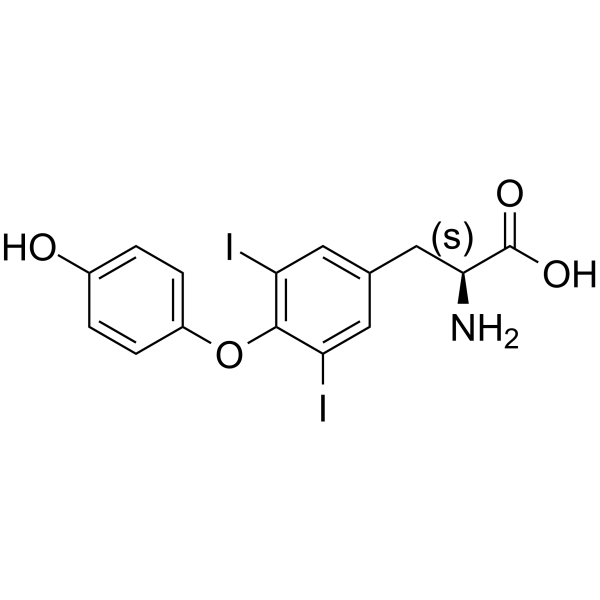
NSC 90469Thyroid Hormone Derivative -
HY-18341S4
L-Thyroxine-13C6-1Stable Isotope -

HY-114557R
NSC 90469 (Standard)Endogenous Metabolite -
HY-115434
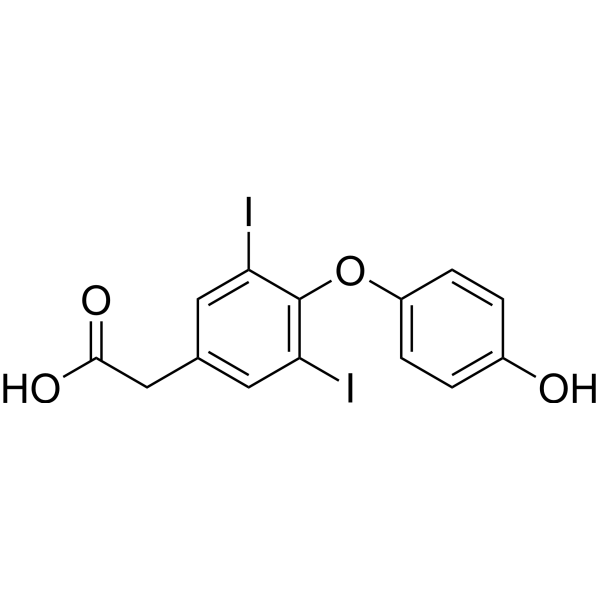
3,5-Diiodothyroacetic acidThyroid Hormone Analog
All Endogenous Metabolite Isoforms
More

Biological Activity
Description
In Vitro
Stable heavy isotopes of hydrogen, carbon, and other elements have been incorporated into drug molecules, largely as tracers for quantitation during the drug development process. Deuteration has gained attention because of its potential to affect the pharmacokinetic and metabolic profiles of drugs[1].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only. Further protocols information, click here.
Application
1. This compound can be used as a tracer
2. This compound can be used as an internal standard for quantitative analysis by NMR, GC-MS, or LC-MS.


Chemical Information
-
CAS No. 720710-30-5
-
Unlabeled CAS 51-48-9
-
Appearance Solid
-
Molecular Weight 782.83
-
Formula C913C6H11I4NO4
-
Color White to off-white
-
SMILES
IC(C=C1O[13C]2=[13C]([13CH]=[13C]([13CH]=[13C]2I)C[C@H](N)C(O)=O)I)=C(C(I)=C1)O
-
Shipping
Room temperature in continental US; may vary elsewhere.
-
Storage
Powder -20°C 3 years 4°C 2 years In solvent -80°C 6 months -20°C 1 month

Protocols
-
Research Protocol for Endocrine Diseases
Endocrine diseases often arise from disrupted hormone production, hormone signaling, or target-tissue responsiveness; for diabetes-focused endocrine disease models, insulin signaling regulates glucose uptake, hepatic glucose output, lipid metabolism, and β-cell compensation. Type 2 diabetes develops through interacting defects in insulin resistance, β-cell dysfunction, adipose inflammation, hepatic glucose overproduction, altered incretin signaling, and ectopic lipid metabolism. A major unresolved question is whether endocrine dysfunction is driven primarily by target-tissue insulin resistance, intrinsic β-cell failure, immune/inflammatory stress, or combined multi-organ failure that differs by disease stage.


Purity & Documentation
-
Data Sheet (266 KB)
-
SDS (393 KB)
- English - EN (393 KB)
- Français - FR (393 KB)
- Deutsch - DE (393 KB)
- Norwegian - NO (393 KB)
- Español - ES (393 KB)
- Swedish - SV (393 KB)
- Italian - IT (393 KB)
- Korean - KR (393 KB)
- Portuguese - PT (393 KB)
-
Handling Instructions (2659 KB)
References
[1]. Russak EM, et al. Impact of Deuterium Substitution on the Pharmacokinetics of Pharmaceuticals. Ann Pharmacother. 2019 Feb;53(2):211-216. [Content Brief]
[2]. Arici M, et al. Association between genetic polymorphism and levothyroxine bioavailability in hypothyroid patients. Endocr J. 2018 Mar 28;65(3):317-323. [Content Brief]
[3]. Corriveau S, et al. Levothyroxine treatment generates an abnormal uterine contractility patterns in an in vitro animalmodel. J Clin Transl Endocrinol. 2015 Sep 92(4):144-149. [Content Brief]

Calculators
Concentration (start) × Volume (start) = Concentration (final) × Volume (final)


L-Thyroxine-13C6 Related Classifications
HY-18341S2 Related Classifications
 Powered by Bioz