



Pelgifatamab

Based on 1 Customer Validation
Peligifatamab is a PSMA-targeted α-radioimmunoconjugate with an EC50 of 1.2 nM against human targets. Peligifatamab induces DNA damage, DNA double-strand breaks, cell cycle arrest and apoptosis (Apoptosis) in PSMA-positive prostate cancer cells. Peligifatamab reduces cell viability in a manner dependent on cellular PSMA expression levels. Peligifatamab inhibits tumor growth and tumor-induced abnormal bone growth in prostate cancer bone metastasis models. Peligifatamab exhibits antitumor efficacy in subcutaneous prostate cancer models and xenograft models. Peligifatamab can be used for the research of metastatic castration-resistant prostate cancer.
For research use only. We do not sell to patients.
- Purity : 99.884%
- CAS No.: 2414550-93-7
- Molecular Weight:146.24 kDa
-
Storage:
Please store the product under the recommended conditions in the Certificate of Analysis.


To place orders, for customer services and technical support, please contact: MedChemExpress USA
Tel: 609-228-6898 E-mail: [email protected] [email protected]


-
 Biological Activity
-
Chemical Information
- Protocols
- Purity & Documentation
- References
-
 Help & FAQs






Biological Activity
Description
Isotype
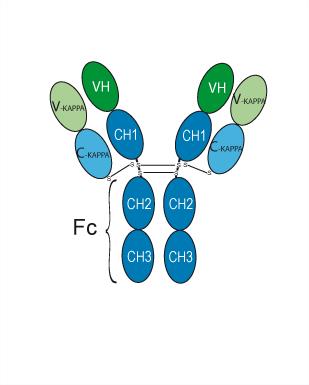
Human IgG1 kappa
Recommend Isotype Controls
Species Reactivity
Human
IC50 & Target
FOLH1/PSMA
In Vivo
Peligifatamab (100-500 kBq/kg; i.v.; single dose) exhibits potent antitumor efficacy in androgen-independent and castration-resistant subcutaneous prostate cancer xenografts, with a T/C ratio as low as 0.09 at a single dose of 500 kBq/kg in MDA-PCa-2b xenografts[1].
Peligifatamab (75-500 kBq/kg; 4×75 kBq/kg; 4×125 kBq/kg; 2×150 kBq/kg; 2×250 kBq/kg; i.v.; single dose; weekly; biweekly) induces potent antitumor efficacy in xenografts of prostate cancer, with a T/C ratio as low as 0.01 in ST1273 xenografts when a single dose of 500 kBq/kg is administered[1].
Peligifatamab (100-200 kBq/kg; i.v.; single dose) potently inhibits tumor growth and tumor-induced bone tissue changes in an intratibial prostate cancer bone metastasis model, with a single dose of 100 kBq/kg resulting in a T/C ratio of 0.03[1].
Peligifatamab (500 kBq/kg; total antibody 0.14-5 mg/kg; i.v.; single dose) maintains potent antitumor efficacy in the 22Rv1 xenograft model when the total antibody dose ranges from 0.14 to 1.5 mg/kg, whereas the efficacy decreases at a total antibody dose of 5 mg/kg[1].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only.
-
Animal Model:CB17-Scid (male)[1]
-
Dosage:75 kBq/kg ; 150 kBq/kg ; 300 kBq/kg; 4 × 75 kBq/kg; 2 × 150 kBq
-
Administration:i.v.; single dose; weekly for 4 doses; biweekly for 2 doses
-
Result:Achieved T/C ratios of 0.51, 0.42, and 0.31 with single doses of 75, 150, and 300 kBq/kg, respectively.
Resulted in 7 of 10 mice showing partial response or stable disease with 300 kBq/kg single dose.
Achieved T/C ratios of 0.07 and 0.12 with fractionated doses of 4 × 75 kBq/kg and 2 × 150 kBq/kg, respectively.
-
Animal Model:athymic nude (male); NMRI Nude (male)[1]
-
Dosage:100 kBq/kg (0.14 mg/kg total antibody); 250 kBq/kg (0.14 mg/kg total antibody); 500 kBq/kg (0.14 mg/kg total antibody)
-
Administration:i.v.; single dose
-
Result:Achieved T/C ratios of 0.33, 0.18, and 0.09 with single doses of 100, 250, and 500 kBq/kg in MDA-PCa-2b xenografts, respectively.
Achieved T/C ratios of 0.54, 0.37, and 0.19 with single doses of 100, 250, and 500 kBq/kg in 22Rv1 xenografts, respectively.
Achieved T/C ratios of 0.27, 0.47, and 0.15 with single doses of 100, 250, and 500 kBq/kg in C4-2 xenografts, respectively.
Induced statistically significant tumor growth inhibition at ≥250 kBq/kg in MDA-PCa-2b and 22Rv1 models, and starting at 100 kBq/kg in the C4-2 model.
-
Animal Model:NMRI nude (female); CB17-Scid (male)[1]
-
Dosage:125 kBq/kg (0.14 mg/kg total antibody); 250 kBq/kg (0.14 mg/kg total antibody); 500 kBq/kg (0.14 mg/kg total antibody); 4 × 125 kBq/kg (0.14 mg/kg total antibody per dose); 2 × 250 kBq/kg (0.14 mg/kg total antibody per dose); 75 kBq/kg (0.14 mg/kg total antibody); 150 kBq/kg (0.14 mg/kg total antibody); 300 kBq/kg (0.14 mg/kg total antibody); 4 × 75 kBq/kg (0.14 mg/kg total antibody per dose); 2 × 150 kBq/kg (0.14 mg/kg total antibody per dose)
-
Administration:i.v.; single dose; weekly for 4 doses; biweekly for 2 doses
-
Result:Achieved T/C ratios of 0.3, 0.05, and 0.01 with single doses of 125, 250, and 500 kBq/kg in ST1273 xenografts, respectively.
Resulted in 5 partial responses and 4 complete responses out of 10 mice with 500 kBq/kg single dose in ST1273 xenografts.
Reduced serum PSA levels effectively with 250 and 500 kBq/kg single doses in ST1273 xenografts.
Achieved T/C ratios of 0.13 and 0.04 with fractionated doses of 4 × 125 kBq/kg and 2 × 250 kBq/kg in ST1273 xenografts, respectively.
Achieved T/C ratios of 0.39, 0.28, and 0.07 with single doses of 75, 150, and 300 kBq/kg in KUCaP-1 xenografts, respectively.
Resulted in 2 stable disease and 6 partial responses out of 10 mice with 300 kBq/kg single dose in KUCaP-1 xenografts.
Achieved T/C ratios of 0.24 and 0.25 with fractionated doses of 4 × 75 kBq/kg and 2 × 150 kBq/kg in KUCaP-1 xenografts, respectively.
Achieved T/C ratios of 0.58 and 0.27 with single doses of 150 and 300 kBq/kg in LuCaP 86.2 xenografts, respectively.
Resulted in 5 stable disease, 1 partial response, and 1 complete response out of 10 mice with 300 kBq/kg single dose in LuCaP 86.2 xenografts.
-
Animal Model:NOD.scid (male)[1]
-
Dosage:100 kBq/kg (0.14 mg/kg total antibody); 200 kBq/kg (0.14 mg/kg total antibody)
-
Administration:i.v.; single dose
-
Result:Reduced LNCaP-luc tumor burden in bone with T/C ratios of 0.03 and 0.14 based on bioluminescence with single doses of 100 and 200 kBq/kg, respectively.
Lowered serum PSA levels with single doses of 100 and 200 kBq/kg.
Significantly inhibited the total area of tumor-induced bone changes compared to vehicle controls with single doses of 100 and 200 kBq/kg.
-
Animal Model:NMRI Nude (male)[1]
-
Dosage:500 kBq/kg (0.14 mg/kg total antibody); 500 kBq/kg (0.75 mg/kg total antibody); 500 kBq/kg (1.5 mg/kg total antibody); 500 kBq/kg (5 mg/kg total antibody)
-
Administration:i.v.; single dose
-
Result:Achieved T/C ratios of 0.13-0.31 with single 500 kBq/kg doses at total antibody doses of 0.14, 0.75, and 1.5 mg/kg.
Resulted in reduced efficacy with a T/C ratio of 0.84 with single 500 kBq/kg dose at 5 mg/kg total antibody dose.
Gene ID
Accession
Conjugated
Unconjugated
Reconsititution
The product can be reconstituted/diluted with sterile PBS or saline.
Format
-
Human IgG1 kappa
Application
ELISA, FACS, Functional assay
Verified Bioactivity
-
 Immobilized PSMA Protein, Human (HEK293, N-His, HY-P70548A) can bind Pelgifatamab. The EC50 for this effect is 107.5 ng/mL.


Chemical Information
-
CAS No. 2414550-93-7
-
Appearance Liquid
-
Molecular Weight 146.24 kDa
-
Color Colorless to light yellow
-
SMILES
[Pelgifatamab]
-
Synonyms
BAY-2315497; PSMA-TTC
-
Shipping
Shipping with dry ice.
-
Formulation
Please refer to the lot-specific COA for specific buffer information.
-
Storage
Please store the product under the recommended conditions in the Certificate of Analysis.

Protocols
-
RNA extraction experimental
By lysing cells, releasing RNA, and removing impurities such as proteins and DNA, high-purity RNA products are finally obtained. The commonly used traditional method is the guanidine isothiocyanate/phenol/chloroform method (Trizol), which is suitable for a variety of animal materials including animal tissues, microorganisms, cultured cells, etc., and most plant materials.
-
Mammalian live/dead viability and cytotoxicity staining
Live/dead viability and cytotoxicity staining assays are based on the simultaneous detection of intracellular esterase activity in metabolically active (viable) cells and membrane integrity loss in non-viable cells. In commonly used dual-staining approaches, membrane-permeant fluorogenic substrates are converted by intracellular esterases into fluorescent products in live cells, while impermeant DNA-binding dyes selectively enter cells with compromised plasma membranes and label nucleic acids in dead or dying cells, enabling discrimination between viable and non-viable populations by fluorescence microscopy or flow cytometry.
-
Annexin V plus membrane-impermeant dye apoptosis staining
Annexin V-based apoptosis assays rely on the detection of phosphatidylserine (PS) externalization from the inner leaflet of the plasma membrane to the outer leaflet, an early biochemical hallmark of apoptosis. Fluorescently labeled Annexin V binds PS in a calcium-dependent manner, enabling identification of early apoptotic cells by flow cytometry or fluorescence microscopy. When combined with a membrane-impermeant DNA-binding dye (e. g. , propidium iodide), this approach allows discrimination between viable (Annexin V−/dye−), early apoptotic (Annexin V+/dye−), and late apoptotic or necrotic (Annexin V+/dye+) cell populations by assessing membrane integrity and PS exposure.
-
BrdU Incorporation Assay
Bromodeoxyuridine (BrdU) incorporation assay is based on the principle that BrdU, a thymidine analog, is incorporated into newly synthesized DNA during the S phase of the cell cycle, thereby serving as a marker of DNA replication and cellular proliferation. Incorporated BrdU can be detected using anti-BrdU antibodies following DNA denaturation, enabling visualization or quantification of proliferating cells through immunochemical detection methods such as immunofluorescence or immunohistochemistry.
-
Patient-Derived Orthotopic Xenograft (PDOX)
Patient-derived orthotopic xenograft (PDOX) modeling implants fresh patient tumor tissue or patient-derived tumor cells into the anatomically corresponding organ or tissue site of immunodeficient mice, usually by surgical orthotopic implantation, to preserve patient tumor histology, local microenvironmental context, invasion, metastatic behavior, and treatment-response features better than subcutaneous implantation. PDOX readouts include tumor engraftment, orthotopic tumor growth, local invasion, metastasis, recurrence after resection, histologic similarity to the donor tumor, biomarker retention, molecular concordance, survival, and response or resistance to therapy. PDOX models are used for preclinical drug testing and individualized therapy evaluation, but engraftment success varies by tumor type and specimen quality.
-
Protocol for Cell Cycle
Cell-cycle analysis by flow cytometry measures DNA content in single cells to estimate the fraction of cells in G0/G1, S, and G2/M phases. Propidium iodide intercalates into DNA, and after RNA removal with RNase, fluorescence intensity reflects cellular DNA content: 2N cells are assigned to G0/G1, cells between 2N and 4N to S phase, and 4N cells to G2/M. DNA-content analysis alone cannot reliably separate G0 from G1 or G2 from M. Ki-67 can distinguish quiescent G0 cells from cycling cells, EdU or BrdU incorporation marks active DNA synthesis in S phase, and phospho-histone H3 staining identifies mitotic cells within the 4N population.
-
CCK-8/WST-8 Cell Proliferation Assay
The CCK-8/WST-8 assay is based on the reduction of the water-soluble tetrazolium salt WST-8 to a water-soluble formazan product by cellular dehydrogenases in metabolically active cells, where the generated formazan amount is proportional to the number of living cells and is quantified by measuring absorbance in the visible range, providing a colorimetric readout for cell viability and proliferation assessment. This class of tetrazolium-based assays improves upon earlier MTT-based systems by producing a water-soluble formazan, eliminating the need for organic solubilization steps and enabling direct spectrophotometric measurement in culture medium.
-
Cell Viability Determination by MTT Colorimetric Assay
The following protocol uses the MTT colorimetric assay as a classic literature-established method for assessing cell viability/metabolic activity in cultured mammalian cells. MTT[3-(4,5-dimethylthiazol-2-yl)-2,5-diphenyltetrazolium bromide] is reduced by metabolically active cells to a colored formazan product; the amount of formazan is quantified spectrophotometrically and provides an indirect measure of metabolically active viable cells. Importantly, MTT reduction reflects cellular oxidoreductase/metabolic activity rather than an absolute direct count of living cells, so changes in cellular metabolism can alter the signal independently of cell number.
-
How to Select the Route of Administration for Mammals
Route-of-administration selection in mammals is a pharmacokinetic, pharmacodynamic, formulation, animal-welfare, and translational decision, not a default technical choice. The selected route should match the study goal: intravenous dosing is most useful when complete systemic exposure and rapid onset are required, oral dosing is most translational for orally intended medicines but is affected by absorption and first-pass metabolism, subcutaneous or intramuscular dosing can provide slower systemic exposure, and intraperitoneal dosing can be useful in rodent proof-of-concept studies but may have limited clinical translation. Published route-comparison studies show that the same compound can produce different exposure, onset, bioavailability, tissue distribution, and tolerability depending on route; therefore, route choice should be supported by pilot pharmacokinetic or pharmacodynamic evidence when the literature is insufficient. Unresolved questions include how to standardize route sel
-
Apoptosis
Apoptosis, also called programmed cell death, is generally characterized by distinct morphological characteristics.
-
TUNEL staining for apoptotic DNA fragmentation
TUNEL staining detects DNA strand breaks by using terminal deoxynucleotidyl transferase to add labeled nucleotides to exposed 3′-OH DNA termini, generating either microscopic staining in fixed cells or tissue sections, or fluorescence/cytometric signal in cell suspensions. TUNEL positivity reflects DNA fragmentation but should not be interpreted alone as definitive apoptosis, because TUNEL can also label necrotic, autolytic, mechanically damaged, or DNA-repair-associated DNA breaks.
-
Flow cytometric DNA-content cell-cycle staining
Flow cytometric DNA-content cell-cycle staining measures the fluorescence intensity of DNA-bound fluorochromes in single cells or nuclei to estimate DNA content distributions, allowing assignment of populations to G0/G1, S, and G2/M phases by DNA histogram deconvolution. Propidium iodide (PI) intercalates into DNA, and PI fluorescence is proportional to cellular DNA content when staining is performed under conditions that make DNA accessible and minimize non-DNA signal. Cells with G2/M DNA content are expected to show approximately twice the fluorescence intensity of G0/G1 cells, while S-phase cells occupy intermediate fluorescence values. PI-based DNA-content analysis can also detect cells with fractional DNA content, often reported as sub-G1, when DNA fragmentation and extraction during staining reduce retained DNA signal in apoptotic cells. DAPI is an alternative DNA fluorochrome for univariate DNA-content analysis, while bivariate approaches combining DNA content with proliferation
-
Cell Cytotoxicity Assay
Cytotoxicity assays are usually based on the assessment of cell membrane damage, which can also be indirectly detected by measuring cell viability. Detection methods include MTT assay, CKK-8 assay, LDH assay and ATP assay, etc.
-
Patient-Derived Xenograft (PDX)
Patient-derived xenograft (PDX) models are generated by engrafting primary human tumor tissue directly into immunodeficient mice, allowing in vivo propagation of patient tumor biology without initial in vitro adaptation. These models are used to preserve key histopathological and molecular characteristics of the original tumor and enable assessment of tumor growth dynamics and therapeutic response in a living organism. The biological readout is tumor engraftment and subsequent growth in the murine host, which reflects the ability of human tumor cells to survive, vascularize, and expand in an immunocompromised microenvironment.
-
Apoptosis Solutions
Apoptosis is a regulated, generally non-lytic cell-death pathway that removes unwanted, damaged, infected, or abnormal cells through coordinated morphological changes, caspase activation, DNA fragmentation, and membrane remodeling. The intrinsic apoptosis pathway is controlled mainly by mitochondrial outer membrane permeabilization, BCL-2 family proteins, cytochrome c release, apoptosome formation, caspase-9 activation, and downstream executioner caspase-3/7 activation. The extrinsic apoptosis pathway is initiated by death receptors such as Fas, TNFR, and TRAIL receptors, which recruit adaptor proteins and activate caspase-8 before engaging executioner caspases or mitochondrial amplification through BID cleavage. Apoptosis is linked to many phenotypes, including cancer cell killing, tissue homeostasis, immune regulation, neurodegeneration, infection response, and treatment-induced cytotoxicity; unresolved questions include how apoptosis interacts with necroptosis, pyroptosis, ferroptos
-
Splenic/Portal-Vein Liver Metastasis Xenograft
Splenic and portal-vein liver metastasis xenograft models deliver tumor cells into the portal circulation so that cells reach the liver first and form hepatic metastatic lesions; splenic injection uses the spleen as an access route to the portal system, while direct portal-vein injection introduces cells into the portal vein without requiring splenectomy. The assay detects liver colonization, intrahepatic tumor growth, tumor distribution, treatment response, survival, and liver-metastasis microenvironment changes; readouts include bioluminescence or fluorescence imaging, gross liver nodule counts, liver weight or tumor burden, histology, and survival.
-
Intracardiac/Intra-Arterial Metastasis Xenograft
Intracardiac xenograft metastasis models are based on the direct delivery of fluorescent or bioluminescent tumor cells into the left ventricle of immunocompromised mice, allowing systemic arterial dissemination that mimics hematogenous spread and enables colonization of distant organs such as bone, brain, and lung. Real-time bioluminescence imaging (BLI) is used to non-invasively track tumor cell seeding, survival, and metastatic outgrowth over time, reflecting early arrest in capillary beds followed by organ-specific colonization and proliferation.
-
MTT Cell Proliferation Assay
The MTT assay is a colorimetric endpoint assay for estimating viable cell number, cell growth, cytotoxicity, or cell activation in cultured mammalian cells. Living cells reduce the yellow tetrazolium salt MTT into purple/blue formazan, while dead cells do not generate the same signal; the resulting color can be quantified with a multiwell spectrophotometer. MTT reduction is commonly interpreted as a readout of metabolic activity that often correlates with viable cell number, but it should not be treated as a direct cell-counting method unless the assay is optimized for the cell type and experimental condition. Studies show that MTT reduction can involve mitochondrial and non-mitochondrial reducing systems, and formazan may accumulate in intracellular lipid droplets rather than simply marking mitochondria.
-
Subcutaneous Cell-Line-Derived Xenograft
Subcutaneous cell-line-derived xenograft (CDX) models are established by implanting cultured human cancer cell lines into immunodeficient mice, where the injected cells form localized tumors that can be monitored in vivo as a measure of tumorigenic potential, growth kinetics, and treatment response. These models are widely used in oncology research because they allow reproducible tumor formation and enable comparative assessment of tumor growth between different cell lines or genetic manipulations in a controlled in vivo microenvironment. Subcutaneous implantation of cancer cells in immunodeficient mice is a standard approach for evaluating tumor growth behavior and therapeutic response across multiple cancer types, including prostate, esophageal, pancreatic, and colon cancer models.
-
Genotoxicity/Mutagenicity Study
The bacterial reverse mutation assay detects point mutations that restore amino-acid prototrophy in auxotrophic Salmonella typhimurium or Escherichia coli tester strains; after exposure to a test article, mutagenic activity is read out as an increased number of revertant colonies on minimal agar compared with the vehicle control. The assay uses tester strains with different mutation targets so that base-substitution and frameshift mutagens can be detected, and testing is performed with and without exogenous mammalian metabolic activation because some chemicals require biotransformation to become mutagenic.
-
Orthotopic Cell-Line Xenograft
Orthotopic cell-line xenograft models involve implantation of human cancer cell lines into the anatomically corresponding organ of immunodeficient mice to reproduce tumor growth within a native microenvironment, enabling more clinically relevant tumor behavior compared with subcutaneous models. These models are widely used because orthotopic placement better recapitulates tumor progression, including invasion and metastatic spread, which are often underrepresented in heterotopic implantation systems. Compared with conventional xenografts, orthotopic implantation is described as more technically complex but provides improved simulation of tumor-microenvironment interactions and metastatic behavior, making it particularly valuable for translational oncology research. Surgical orthotopic implantation approaches have been emphasized as enabling faithful reproduction of clinical cancer features, including metastasis and disease progression patterns that align with the tumor’s organ of origi
-
Intraperitoneal/Peritoneal Dissemination Xenograft
Intraperitoneal (IP) or peritoneal dissemination xenograft models are based on the introduction of human cancer cells into the peritoneal cavity of immunodeficient mice, where they attach to peritoneal surfaces, form multicellular aggregates or spheroids, and progressively generate disseminated tumor nodules that mimic advanced peritoneal metastatic disease. These models are widely used to study ovarian cancer progression, tumor-microenvironment interactions, and intraperitoneal therapeutic responses, often incorporating bioluminescence or fluorescence imaging to longitudinally monitor tumor burden in vivo. The biological principle relies on the capacity of tumor cells such as SKOV3 or related ovarian carcinoma lines to survive in suspension, aggregate within ascites-like fluid, adhere to mesothelial surfaces, and invade peritoneal organs, thereby recapitulating human peritoneal carcinomatosis patterns observed in advanced disease.


Purity & Documentation
-
Data Sheet (265 KB)
-
SDS (252 KB)
- English - EN (252 KB)
- Français - FR (252 KB)
- Deutsch - DE (252 KB)
- Norwegian - NO (252 KB)
- Español - ES (252 KB)
- Swedish - SV (252 KB)
- Italian - IT (252 KB)
- Korean - KR (252 KB)
- Portuguese - PT (252 KB)
-
Inhibitory Antibodies User Guide (603 KB)
References

Calculators
Concentration (start) × Volume (start) = Concentration (final) × Volume (final)


Pelgifatamab Related Classifications
HY-P9992 Related Classifications
 Powered by Bioz