



JNJ-1250132
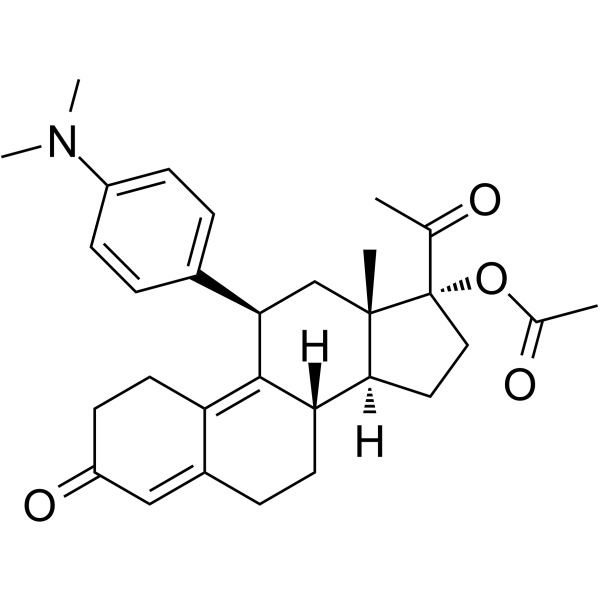
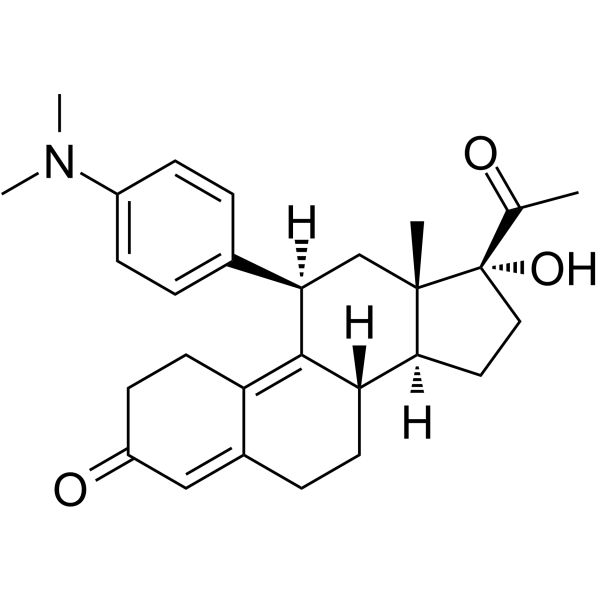
JNJ-1250132 (RWJ-66826) is an orally active and potent steroidal progesterone receptor (PR) antagonist, with an IC50 of 1.3 nM. JNJ-1250132 inhibits binding of the receptor to DNA in vitro. JNJ-1250132 is a potent competitive inhibitor of binding to the human glucocorticoid receptor (GR) (IC50=0.50 nM) and the rat androgen receptor (AR) (IC50=5.6 nM), and was a weak inhibitor of binding to human Estrogen receptor (ER) (IC50 >3000 nM).
For research use only. We do not sell to patients.
- CAS No.: 240805-96-3
- Formula: C33H41NO4
- Molecular Weight:515.68
-
Storage:
Please store the product under the recommended conditions in the Certificate of Analysis.


To place orders, for customer services and technical support, please contact: MedChemExpress USA
Tel: 609-228-6898 E-mail: [email protected] [email protected]


-
 Biological Activity
-
Chemical Information
- Protocols
- Purity & Documentation
- References
-
 Help & FAQs




Biological Activity
Description
In Vitro
JNJ-1250132 and Mifepristone (HY-13683) inhibits R5020 (HY-119384)-stimulated cell proliferation at similar half-maximal inhibitory concentrations (IC50s of 0.19 nM and 0.17 nM, respectively)[1].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only. Further protocols information, click here.
In Vivo
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only.


Chemical Information
-
CAS No. 240805-96-3
-
Molecular Weight 515.68
-
Formula C33H41NO4
-
SMILES
CC([C@@]1(OC(C)=O)CC[C@@]2([H])[C@]3([H])CCC4=CC(CCC4=C3[C@@H](C5=CC=C(N6CCCCC6)C=C5)C[C@]12C)=O)=O
-
Synonyms
RWJ-66826; RTI-6617-003
-
Shipping
Room temperature in continental US; may vary elsewhere.
-
Storage
Please store the product under the recommended conditions in the Certificate of Analysis.

Protocols
-
Cell Cytotoxicity Assay
Cytotoxicity assays are usually based on the assessment of cell membrane damage, which can also be indirectly detected by measuring cell viability. Detection methods include MTT assay, CKK-8 assay, LDH assay and ATP assay, etc.
-
Research Protocol for Endocrine Diseases
Endocrine diseases often arise from disrupted hormone production, hormone signaling, or target-tissue responsiveness; for diabetes-focused endocrine disease models, insulin signaling regulates glucose uptake, hepatic glucose output, lipid metabolism, and β-cell compensation. Type 2 diabetes develops through interacting defects in insulin resistance, β-cell dysfunction, adipose inflammation, hepatic glucose overproduction, altered incretin signaling, and ectopic lipid metabolism. A major unresolved question is whether endocrine dysfunction is driven primarily by target-tissue insulin resistance, intrinsic β-cell failure, immune/inflammatory stress, or combined multi-organ failure that differs by disease stage.


Purity & Documentation
References

Calculators
Concentration (start) × Volume (start) = Concentration (final) × Volume (final)


JNJ-1250132 Related Classifications
HY-123163 Related Classifications
 Powered by Bioz