



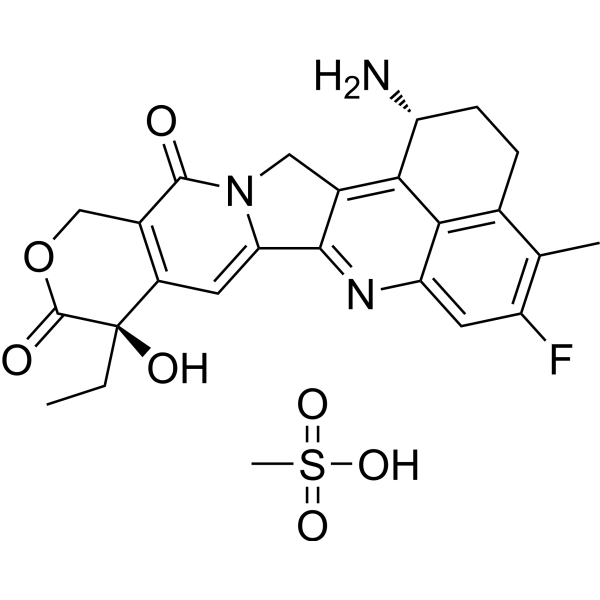
(1R,9R)-Exatecan mesylate

Based on 1 Customer Validation
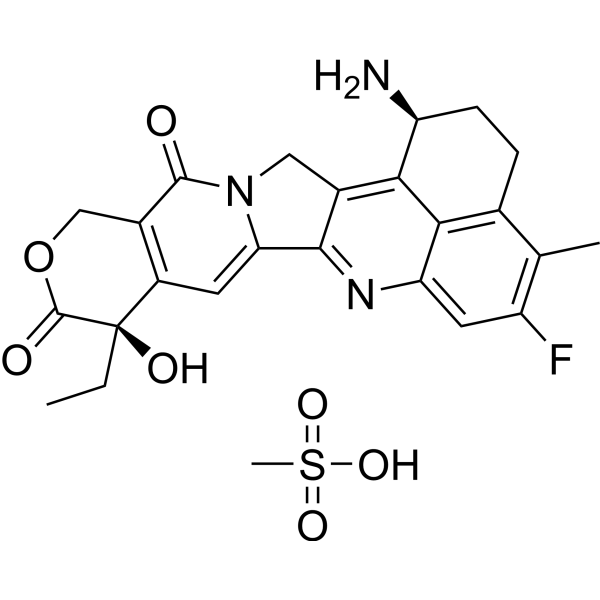
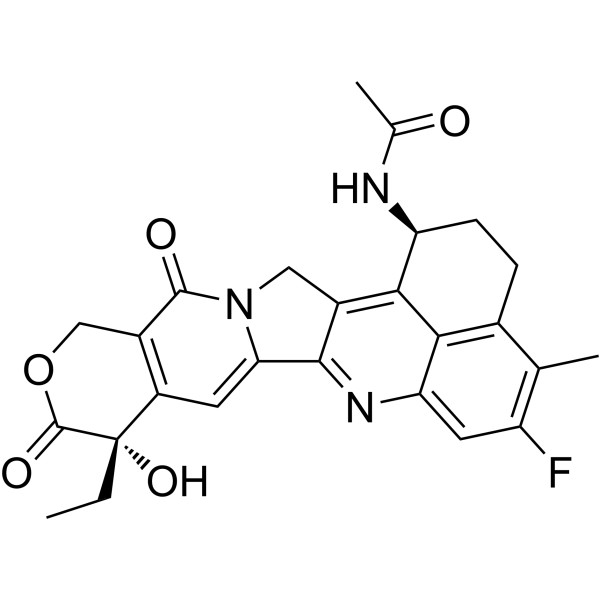
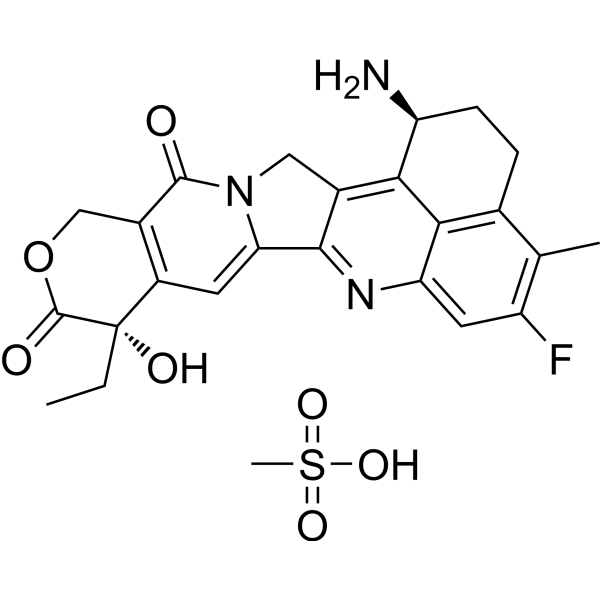
(1R,9R)-Exatecan mesylate ((1R,9R)-DX8951f) is a non-prodrug camptothecin derivative and a potent topoisomerase I inhibitor (IC50=0.975 μg/mL in mice and 0.82 μg/mL in humans). (1R,9R)-Exatecan mesylate blocks enzyme activity and induces apoptosis by stabilizing the enzyme-DNA cleavable complex. (1R,9R)-Exatecan mesylate not only effectively inhibits the proliferation of various malignant tumor cells and tumor growth, but also circumvents P-glycoprotein-mediated multidrug resistance. (1R,9R)-Exatecan mesylate is widely used in preclinical studies of multiple cancers including pancreatic cancer, lung cancer, breast cancer, and leukemia. The low-activity isomer of (1R,9R)-Exatecan mesylate is (1S,9R)-Exatecan mesylate (HY-13631I).
For research use only. We do not sell to patients.
- Purity : 99.49%
- CAS No.: 2938875-39-7
- Formula: C25H26FN3O7S
- Molecular Weight:531.55
-
Storage:
4°C, stored under nitrogen, away from moisture
* In solvent : -80°C, 6 months; -20°C, 1 month (stored under nitrogen, away from moisture)

To place orders, for customer services and technical support, please contact: MedChemExpress USA
Tel: 609-228-6898 E-mail: [email protected] [email protected]


-
 Biological Activity
-
Chemical Information
-
Solvent & Solubility
- Protocols
- Purity & Documentation
- References
-
 Help & FAQs


All Topoisomerase Isoforms
More

Biological Activity
Description
IC50 & Target
|
Camptothecins |
In Vitro
(1R,9R)-Exatecan mesylate potently inhibits the growth of SUIT-2 and KP-1N human pancreatic cancer cell lines in vitro, with 48 h IC50 values of 0.079 ng/mL and 0.12 ng/mL, respectively[1].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only. Further protocols information, click here.
In Vivo
(1R,9R)-Exatecan (mesylate) (18.75 mg/kg; i.v.; once every 4 days; 4 doses) achieves a 72% tumor growth inhibition rate against CPT-11-resistant SUIT-2/CPT-11 pancreatic cancer xenografts in nude mice at its maximum tolerable dose[1].
(1R,9R)-Exatecan (mesylate) (2.5-10 mg/kg; i.v.; once every 5 days; 4 doses) dose-dependently inhibits liver metastasis of SUIT-2 pancreatic cancer in nude mice, achieving a 78% liver tumor growth score inhibition rate and 100% ascites inhibition at a total dose of 40 mg/kg[1].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only.
-
Animal Model:BALB/c-nu/nu (male, 6 weeks old, subcutaneous xenograft of human pancreatic carcinoma SUIT-2 cells)[1]
-
Dosage:3.125 mg/kg (total 12.5 mg/kg); 6.25 mg/kg (total 25 mg/kg); 12.5 mg/kg (total 50 mg/kg); 18.75 mg/kg (total 75 mg/kg)
-
Administration:i.v.; once every 4 days; 4 doses
-
Result:Achieved a 79% tumor growth inhibition rate with mean tumor weight of 0.154 ± 0.027 g at total dose 75 mg/kg.
Achieved a 68% tumor growth inhibition rate with mean tumor weight of 0.236 ± 0.100 g at total dose 50 mg/kg.
Achieved a 78% tumor growth inhibition rate with mean tumor weight of 0.164 ± 0.053 g at total dose 25 mg/kg.
Achieved a 68% tumor growth inhibition rate with mean tumor weight of 0.235 ± 0.057 g at total dose 12.5 mg/kg.
Caused no body weight loss in any treated group.
-
Animal Model:BALB/c-nu/nu (male, 6 weeks old, subcutaneous xenograft of CPT-11-resistant human pancreatic carcinoma SUIT-2/CPT-11 cells)[1]
-
Dosage:3.125 mg/kg (total 12.5 mg/kg); 6.25 mg/kg (total 25 mg/kg); 12.5 mg/kg (total 50 mg/kg); 18.75 mg/kg (total 75 mg/kg)
-
Administration:i.v.; once every 4 days; 4 doses
-
Result:Achieved a 72% tumor growth inhibition rate with mean tumor weight of 0.250 ± 0.061 g at total dose 75 mg/kg; caused maximum body weight loss of 14.6% on day 31.
Achieved a 33% tumor growth inhibition rate with mean tumor weight of 0.595 ± 0.130 g at total dose 50 mg/kg; caused maximum body weight loss of 6.1% on day 21.
Achieved a 13% tumor growth inhibition rate with mean tumor weight of 0.776 ± 0.157 g at total dose 25 mg/kg; caused maximum body weight loss of 8.7% on day 15.
Achieved a 20% tumor growth inhibition rate with mean tumor weight of 0.712 ± 0.065 g at total dose 12.5 mg/kg; caused maximum body weight loss of 3.2% on day 15.
Caused no treatment-related deaths in any group.
-
Animal Model:BALB/c-nu/nu (male, 6 weeks old, liver metastasis model via intrasplenic injection of human pancreatic carcinoma SUIT-2 cells)[1]
-
Dosage:2.5 mg/kg (total 10 mg/kg); 5 mg/kg (total 20 mg/kg); 10 mg/kg (total 40 mg/kg)
-
Administration:i.v.; once every 5 days; 4 doses
-
Result:Achieved a 78% liver tumor growth score inhibition rate with mean liver tumor growth score of 0.7 ± 0.9, 3/7 liver tumor incidence, mean liver weight of 1.594 ± 0.154 g, 2/7 spleen tumor incidence, 100% ascites inhibition with 0.0 ± 0.0 mL ascites volume, 0/7 ascites incidence, and 3/7 tumor-free mice at total dose 40 mg/kg.
Achieved a 69% liver tumor growth score inhibition rate with mean liver tumor growth score of 1.0 ± 0.6, 5/6 liver tumor incidence, mean liver weight of 1.594 ± 0.163 g, 2/6 spleen tumor incidence, 100% ascites inhibition with 0.0 ± 0.0 mL ascites volume, 0/6 ascites incidence, and 1/6 tumor-free mice at total dose 20 mg/kg.
Achieved a 28% liver tumor growth score inhibition rate with mean liver tumor growth score of 2.3 ± 1.1, 6/6 liver tumor incidence, mean liver weight of 1.780 ± 0.197 g, 3/6 spleen tumor incidence, 97% ascites inhibition with 0.1 ± 0.1 mL ascites volume, and 2/6 ascites incidence at total dose 10 mg/kg.


Chemical Information
-
CAS No. 2938875-39-7
-
Appearance Solid
-
Molecular Weight 531.55
-
Formula C25H26FN3O7S
-
Color Gray to brown
-
SMILES
O=S(C)(O)=O.O=C1[C@@](O)(CC)C2=C(CO1)C(N3CC4=C5C6=C(CC[C@H]5N)C(C)=C(F)C=C6N=C4C3=C2)=O
-
Synonyms
(1R,9R)-DX8951f
-
Shipping
Room temperature in continental US; may vary elsewhere.
-
Storage
4°C, stored under nitrogen, away from moisture
* In solvent : -80°C, 6 months; -20°C, 1 month (stored under nitrogen, away from moisture)


Solvent & Solubility
In Vitro:
DMSO : 16.67 mg/mL (31.36 mM; Need ultrasonic; Hygroscopic DMSO has a significant impact on the solubility of product, please use newly opened DMSO)
Please refer to the solubility information to select the appropriate solvent. Once prepared, please aliquot and store the solution to prevent product inactivation from repeated freeze-thaw cycles.
Storage method and period of stock solution: -80°C, 6 months; -20°C, 1 month (stored under nitrogen, away from moisture). When stored at -80°C, please use it within 6 months. When stored at -20°C, please use it within 1 month.
Concentration (start) × Volume (start) = Concentration (final) × Volume (final)

Protocols
-
Apoptosis
Apoptosis, also called programmed cell death, is generally characterized by distinct morphological characteristics.
-
TUNEL staining for apoptotic DNA fragmentation
TUNEL staining detects DNA strand breaks by using terminal deoxynucleotidyl transferase to add labeled nucleotides to exposed 3′-OH DNA termini, generating either microscopic staining in fixed cells or tissue sections, or fluorescence/cytometric signal in cell suspensions. TUNEL positivity reflects DNA fragmentation but should not be interpreted alone as definitive apoptosis, because TUNEL can also label necrotic, autolytic, mechanically damaged, or DNA-repair-associated DNA breaks.
-
Cell Cytotoxicity Assay
Cytotoxicity assays are usually based on the assessment of cell membrane damage, which can also be indirectly detected by measuring cell viability. Detection methods include MTT assay, CKK-8 assay, LDH assay and ATP assay, etc.
-
Annexin V plus membrane-impermeant dye apoptosis staining
Annexin V-based apoptosis assays rely on the detection of phosphatidylserine (PS) externalization from the inner leaflet of the plasma membrane to the outer leaflet, an early biochemical hallmark of apoptosis. Fluorescently labeled Annexin V binds PS in a calcium-dependent manner, enabling identification of early apoptotic cells by flow cytometry or fluorescence microscopy. When combined with a membrane-impermeant DNA-binding dye (e. g. , propidium iodide), this approach allows discrimination between viable (Annexin V−/dye−), early apoptotic (Annexin V+/dye−), and late apoptotic or necrotic (Annexin V+/dye+) cell populations by assessing membrane integrity and PS exposure.
-
Patient-Derived Xenograft (PDX)
Patient-derived xenograft (PDX) models are generated by engrafting primary human tumor tissue directly into immunodeficient mice, allowing in vivo propagation of patient tumor biology without initial in vitro adaptation. These models are used to preserve key histopathological and molecular characteristics of the original tumor and enable assessment of tumor growth dynamics and therapeutic response in a living organism. The biological readout is tumor engraftment and subsequent growth in the murine host, which reflects the ability of human tumor cells to survive, vascularize, and expand in an immunocompromised microenvironment.
-
Apoptosis Solutions
Apoptosis is a regulated, generally non-lytic cell-death pathway that removes unwanted, damaged, infected, or abnormal cells through coordinated morphological changes, caspase activation, DNA fragmentation, and membrane remodeling. The intrinsic apoptosis pathway is controlled mainly by mitochondrial outer membrane permeabilization, BCL-2 family proteins, cytochrome c release, apoptosome formation, caspase-9 activation, and downstream executioner caspase-3/7 activation. The extrinsic apoptosis pathway is initiated by death receptors such as Fas, TNFR, and TRAIL receptors, which recruit adaptor proteins and activate caspase-8 before engaging executioner caspases or mitochondrial amplification through BID cleavage. Apoptosis is linked to many phenotypes, including cancer cell killing, tissue homeostasis, immune regulation, neurodegeneration, infection response, and treatment-induced cytotoxicity; unresolved questions include how apoptosis interacts with necroptosis, pyroptosis, ferroptos
-
Patient-Derived Orthotopic Xenograft (PDOX)
Patient-derived orthotopic xenograft (PDOX) modeling implants fresh patient tumor tissue or patient-derived tumor cells into the anatomically corresponding organ or tissue site of immunodeficient mice, usually by surgical orthotopic implantation, to preserve patient tumor histology, local microenvironmental context, invasion, metastatic behavior, and treatment-response features better than subcutaneous implantation. PDOX readouts include tumor engraftment, orthotopic tumor growth, local invasion, metastasis, recurrence after resection, histologic similarity to the donor tumor, biomarker retention, molecular concordance, survival, and response or resistance to therapy. PDOX models are used for preclinical drug testing and individualized therapy evaluation, but engraftment success varies by tumor type and specimen quality.
-
Subcutaneous Cell-Line-Derived Xenograft
Subcutaneous cell-line-derived xenograft (CDX) models are established by implanting cultured human cancer cell lines into immunodeficient mice, where the injected cells form localized tumors that can be monitored in vivo as a measure of tumorigenic potential, growth kinetics, and treatment response. These models are widely used in oncology research because they allow reproducible tumor formation and enable comparative assessment of tumor growth between different cell lines or genetic manipulations in a controlled in vivo microenvironment. Subcutaneous implantation of cancer cells in immunodeficient mice is a standard approach for evaluating tumor growth behavior and therapeutic response across multiple cancer types, including prostate, esophageal, pancreatic, and colon cancer models.
-
Breast Cancer Modeling
Breast cancer is a heterogeneous cancer, and it has been distinguished into four subtypes: luminal A, luminal B, HER2-positive and basal-like. Molecular mutations, epigenetic alterations, hormone exposure and immune microenvironment are related to the progression of breast cancer.
-
Orthotopic Cell-Line Xenograft
Orthotopic cell-line xenograft models involve implantation of human cancer cell lines into the anatomically corresponding organ of immunodeficient mice to reproduce tumor growth within a native microenvironment, enabling more clinically relevant tumor behavior compared with subcutaneous models. These models are widely used because orthotopic placement better recapitulates tumor progression, including invasion and metastatic spread, which are often underrepresented in heterotopic implantation systems. Compared with conventional xenografts, orthotopic implantation is described as more technically complex but provides improved simulation of tumor-microenvironment interactions and metastatic behavior, making it particularly valuable for translational oncology research. Surgical orthotopic implantation approaches have been emphasized as enabling faithful reproduction of clinical cancer features, including metastasis and disease progression patterns that align with the tumor’s organ of origi
-
Cell Viability Determination by MTT Colorimetric Assay
The following protocol uses the MTT colorimetric assay as a classic literature-established method for assessing cell viability/metabolic activity in cultured mammalian cells. MTT[3-(4,5-dimethylthiazol-2-yl)-2,5-diphenyltetrazolium bromide] is reduced by metabolically active cells to a colored formazan product; the amount of formazan is quantified spectrophotometrically and provides an indirect measure of metabolically active viable cells. Importantly, MTT reduction reflects cellular oxidoreductase/metabolic activity rather than an absolute direct count of living cells, so changes in cellular metabolism can alter the signal independently of cell number.


Purity & Documentation
-
Data Sheet (286 KB)
-
SDS (252 KB)
- English - EN (252 KB)
- Français - FR (252 KB)
- Deutsch - DE (252 KB)
- Norwegian - NO (252 KB)
- Español - ES (252 KB)
- Swedish - SV (252 KB)
- Italian - IT (252 KB)
- Korean - KR (252 KB)
- Portuguese - PT (252 KB)
-
Handling Instructions (2659 KB)
References
[1]. Takiguchi S, et al. Antitumor effect of DX-8951, a novel camptothecin analog, on human pancreatic tumor cells and their CPT-11-resistant variants cultured in vitro and xenografted into nude mice. Jpn J Cancer Res. 1997;88(8):760-769. [Content Brief]
[2]. Mitsui I, et al. A new water-soluble camptothecin derivative, DX-8951f, exhibits potent antitumor activity against human tumors in vitro and in vivo. Jpn J Cancer Res. 1995;86(8):776-782. [Content Brief]


Complete Stock Solution Preparation Table
Please refer to the solubility information to select the appropriate solvent. Once prepared, please aliquot and store the solution to prevent product inactivation from repeated freeze-thaw cycles.
Storage method and period of stock solution: -80°C, 6 months; -20°C, 1 month (stored under nitrogen, away from moisture). When stored at -80°C, please use it within 6 months. When stored at -20°C, please use it within 1 month.
| Optional Solvent | Concentration Solvent Mass | 1 mg | 5 mg | 10 mg | 25 mg |
|---|---|---|---|---|---|
| DMSO | 1 mM | 1.8813 mL | 9.4065 mL | 18.8129 mL | 47.0323 mL |
| 5 mM | 0.3763 mL | 1.8813 mL | 3.7626 mL | 9.4065 mL | |
| 10 mM | 0.1881 mL | 0.9406 mL | 1.8813 mL | 4.7032 mL | |
| 15 mM | 0.1254 mL | 0.6271 mL | 1.2542 mL | 3.1355 mL | |
| 20 mM | 0.0941 mL | 0.4703 mL | 0.9406 mL | 2.3516 mL | |
| 25 mM | 0.0753 mL | 0.3763 mL | 0.7525 mL | 1.8813 mL | |
| 30 mM | 0.0627 mL | 0.3135 mL | 0.6271 mL | 1.5677 mL |


(1R,9R)-Exatecan mesylate Related Classifications
HY-13631J Related Classifications
 Powered by Bioz