



PSMα3

Based on 1 Customer Validation
PSMα3 is an inhibitor of NF-κB p65 and p38 MAPK. PSMα3 forms membrane pores and binds to residues of human insulin B chain to inhibit insulin aggregation. PSMα3 forms α-type amyloid-like fibrils to exert cytotoxic effects, and acts as a functional amyloid virulence determinant of Staphylococcus aureus. PSMα3 is applicable to research related to spondyloarthritis, rheumatoid arthritis, insulin-derived amyloidosis, and Staphylococcus aureus infection.
For research use only. We do not sell to patients.
- Purity : 99.39%
- CAS No.: 1001405-52-2
- Formula: C128H192N28O30S
- Molecular Weight:2635.13
-
Storage:
Sealed storage, away from moisture and light.
Powder -80°C, 2 years , -20°C, 1 year* In solvent : -80°C, 6 months; -20°C, 1 month (sealed storage, away from moisture and light)
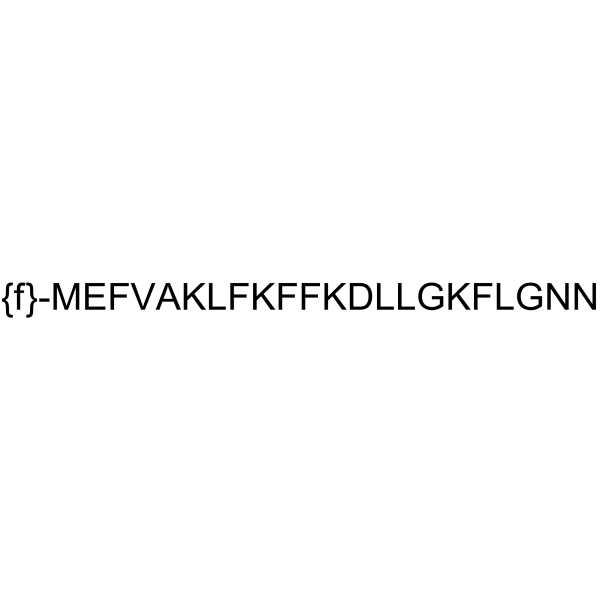

To place orders, for customer services and technical support, please contact: MedChemExpress USA
Tel: 609-228-6898 E-mail: [email protected] [email protected]


-
 Biological Activity
-
Chemical Information
-
Solvent & Solubility
- Protocols
- Purity & Documentation
- References
-
 Help & FAQs




Biological Activity
Description
In Vitro
PSMα3 (10 μM; 6-24 h) alters surface molecule expression in TLR4-stimulated human moDCs, enhancing early HLA-DR expression and reducing CD40 and CD80 expression at 6 and 24 h, respectively, while showing a trend to reduce PD-L1 upregulation at 24 h[1].
PSMα3 (10 μM; 6-24 h) significantly impairs pro- and anti-inflammatory cytokine secretion by TLR4-stimulated human moDCs, reducing TNF, IL-12, and IL-10 production at 6 and 24 h, respectively[1].
PSMα3 (10 μM; 1 h) reduces NF-κB and p38 phosphorylation in a non-significant trend in TLR4-stimulated human moDCs after 1 h of treatment[1].
PSMα3 (10 μM; 24 h) significantly reduces OVA uptake by immature human moDCs after 24 h of treatment, and shows a non-significant trend to further reduce OVA uptake in TLR2- or TLR4-stimulated moDCs[1].
PSMα3 (2.5-10 μM; 10 min) induces concentration-dependent transient pore formation in human moDCs after 10 min of treatment, as measured by LDH release, without reducing cell viability[1].
PSMα3 (10 μM; 24 h moDC pretreatment) in combination with TLR2/TLR4 ligands reduces the frequency of T-bet+ Th1 cells and IFN-γ secretion in co-cultured human naïve CD4+ T cells, while increasing IL-13 secretion when used to pretreat moDCs[1].
PSMα3 (10 μM; 1-2 d) significantly increases IDO production by TLR4-stimulated human moDCs after 1 and 2 d of treatment[1].
Synthetic PSMα3 (0.0625-10 mg/mL; up to 7 days) maintains a stable α-helical conformation in aqueous solution and does not form amyloid fibrils after incubation for up to 7 days at 37 °C, with only minor oligomer formation observed under specific non-standard pre-treatment and incubation conditions[2].
PSMα3 forms a unique cross-α amyloid-like fibril structure, solved at 1.45 Å resolution, with amphipathic α-helices stacked perpendicular to the fibril axis into tight self-associating sheets[3].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only. Further protocols information, click here.


Chemical Information
-
CAS No. 1001405-52-2
-
Appearance Solid
-
Molecular Weight 2635.13
-
Formula C128H192N28O30S
-
Color White to off-white
-
Sequence
{f}-Met-Glu-Phe-Val-Ala-Lys-Leu-Phe-Lys-Phe-Phe-Lys-Asp-Leu-Leu-Gly-Lys-Phe-Leu-Gly-Asn-Asn
-
Sequence Shortening
{f}-MEFVAKLFKFFKDLLGKFLGNN
-
Structure Classification
-
Initial Source
S. aureus
-
Shipping
Room temperature in continental US; may vary elsewhere.
-
Storage
Sealed storage, away from moisture and light
Powder -80°C 2 years -20°C 1 year * In solvent : -80°C, 6 months; -20°C, 1 month (sealed storage, away from moisture and light)


Solvent & Solubility
In Vitro:
DMSO : 100 mg/mL (37.95 mM; Need ultrasonic; Hygroscopic DMSO has a significant impact on the solubility of product, please use newly opened DMSO)
Please refer to the solubility information to select the appropriate solvent. Once prepared, please aliquot and store the solution to prevent product inactivation from repeated freeze-thaw cycles.
Storage method and period of stock solution: -80°C, 6 months; -20°C, 1 month (sealed storage, away from moisture and light). When stored at -80°C, please use it within 6 months. When stored at -20°C, please use it within 1 month.
Concentration (start) × Volume (start) = Concentration (final) × Volume (final)

Protocols
-
Collagen-Induced Arthritis
Collagen-induced arthritis (CIA) is an autoimmune murine model of rheumatoid arthritis in which immunization with type II collagen (CII) emulsified in an adjuvant induces a T cell- and autoantibody-driven inflammatory arthritis characterized by synovial hyperplasia, immune cell infiltration, and joint destruction. The model typically relies on genetically susceptible mouse strains (e. g. , DBA/1) and reproduces key features of human rheumatoid arthritis, including anti-collagen immune responses and progressive joint inflammation. Disease onset generally occurs within ~3-4 weeks after immunization, depending on antigen/adjuvant combinations and protocol variation. The immunopathology is driven by adaptive immune activation against CII, leading to systemic and local joint inflammation mediated by pro-inflammatory cytokines and effector immune cells, making CIA a standard preclinical platform for evaluating immunomodulatory and anti-arthritic interventions.
-
Research Protocol for Infectious Diseases
Infectious-disease experiments test how pathogens interact with host barriers, innate immune receptors, inflammatory signaling, pathogen replication, and tissue injury; pattern-recognition receptors such as TLRs, RIG-I-like receptors, NOD-like receptors, and inflammasomes detect microbial molecules and activate NF-κB, interferon, and cytokine responses. The central hypothesis is that infection severity reflects the balance between pathogen burden and host response: protective inflammation restricts pathogen growth, whereas excessive or mislocalized inflammation contributes to tissue damage and disease phenotype. Unresolved questions include which host pathways are protective versus pathogenic, why some infection models fail to translate to human disease, and which combined readouts best predict clinically relevant infection outcomes.
-
Research Protocol for Endocrine Diseases
Endocrine diseases often arise from disrupted hormone production, hormone signaling, or target-tissue responsiveness; for diabetes-focused endocrine disease models, insulin signaling regulates glucose uptake, hepatic glucose output, lipid metabolism, and β-cell compensation. Type 2 diabetes develops through interacting defects in insulin resistance, β-cell dysfunction, adipose inflammation, hepatic glucose overproduction, altered incretin signaling, and ectopic lipid metabolism. A major unresolved question is whether endocrine dysfunction is driven primarily by target-tissue insulin resistance, intrinsic β-cell failure, immune/inflammatory stress, or combined multi-organ failure that differs by disease stage.
-
Research Protocol for Inflammation-related Diseases
The NLRP3 inflammasome is a cytosolic innate immune signaling platform that integrates priming signals and danger-signal activation to promote caspase-1 activation, maturation of IL-1β and IL-18, and gasdermin D-mediated pyroptotic cell death. The core experimental logic is to determine whether inflammatory disease phenotypes are driven by increased NLRP3 expression, ASC-containing inflammasome assembly, caspase-1 cleavage, GSDMD cleavage, and extracellular release of IL-1β/IL-18 rather than by nonspecific cell injury alone. The pathway is strongly linked to inflammation-related disease phenotypes because monosodium urate crystals activate NALP3/NLRP3 inflammasome signaling in gout-like crystal inflammation, cholesterol crystals activate NLRP3 inflammasomes in atherogenesis models, and DSS-induced intestinal inflammation has been reported to involve NLRP3 inflammasome activity. However, experimental colitis studies also show context-dependent protective effects of NLRP3 inflammasome co
-
Amyloid: Congo Red Amyloid Staining
Congo red amyloid staining is a histochemical method used to detect extracellular amyloid deposits in tissue sections based on the affinity of Congo red dye for β-pleated sheet-rich protein aggregates. When bound to amyloid, Congo red produces characteristic apple-green birefringence under polarized light microscopy, which is widely regarded as a diagnostic feature of amyloid deposition in histopathology. The diagnostic principle relies on the combination of dye binding (congophilia) and optical anisotropy under polarized illumination, which distinguishes amyloid from most non-amyloid eosinophilic extracellular deposits in routine histological evaluation. Amyloid identification by Congo red staining remains a cornerstone in diagnostic pathology despite the availability of adjunct methods such as immunohistochemistry and mass spectrometry, particularly because of its ability to localize deposits directly within tissue architecture. The specificity of Congo red-positive deposits is incre
-
Cell Viability Determination by MTT Colorimetric Assay
The following protocol uses the MTT colorimetric assay as a classic literature-established method for assessing cell viability/metabolic activity in cultured mammalian cells. MTT[3-(4,5-dimethylthiazol-2-yl)-2,5-diphenyltetrazolium bromide] is reduced by metabolically active cells to a colored formazan product; the amount of formazan is quantified spectrophotometrically and provides an indirect measure of metabolically active viable cells. Importantly, MTT reduction reflects cellular oxidoreductase/metabolic activity rather than an absolute direct count of living cells, so changes in cellular metabolism can alter the signal independently of cell number.


Purity & Documentation
-
Data Sheet (271 KB)
-
SDS (252 KB)
- English - EN (252 KB)
- Français - FR (252 KB)
- Deutsch - DE (252 KB)
- Norwegian - NO (252 KB)
- Español - ES (252 KB)
- Swedish - SV (252 KB)
- Italian - IT (252 KB)
- Korean - KR (252 KB)
- Portuguese - PT (252 KB)
-
Handling Instructions (2659 KB)
References
[1]. Richardson JR, et al. Staphylococcus aureus PSM Peptides Modulate Human Monocyte-Derived Dendritic Cells to Prime Regulatory T Cells. Front Immunol. 2018 Nov 13;9:2603. [Content Brief]
[2]. Kalitnik A, et al. Cytotoxic Staphylococcus aureus PSMα3 inhibits the aggregation of human insulin in vitro. Phys Chem Chem Phys. 2024 May 29;26(21):15587-15599. [Content Brief]
[3]. Tayeb-Fligelman E, et al. The cytotoxic Staphylococcus aureus PSMα3 reveals a cross-α amyloid-like fibril. Science. 2017 Feb 24;355(6327):831-833. [Content Brief]


Complete Stock Solution Preparation Table
Please refer to the solubility information to select the appropriate solvent. Once prepared, please aliquot and store the solution to prevent product inactivation from repeated freeze-thaw cycles.
Storage method and period of stock solution: -80°C, 6 months; -20°C, 1 month (sealed storage, away from moisture and light). When stored at -80°C, please use it within 6 months. When stored at -20°C, please use it within 1 month.
| Optional Solvent | Concentration Solvent Mass | 1 mg | 5 mg | 10 mg | 25 mg |
|---|---|---|---|---|---|
| DMSO | 1 mM | 0.3795 mL | 1.8974 mL | 3.7949 mL | 9.4872 mL |
| 5 mM | 0.0759 mL | 0.3795 mL | 0.7590 mL | 1.8974 mL | |
| 10 mM | 0.0379 mL | 0.1897 mL | 0.3795 mL | 0.9487 mL | |
| 15 mM | 0.0253 mL | 0.1265 mL | 0.2530 mL | 0.6325 mL | |
| 20 mM | 0.0190 mL | 0.0949 mL | 0.1897 mL | 0.4744 mL | |
| 25 mM | 0.0152 mL | 0.0759 mL | 0.1518 mL | 0.3795 mL | |
| 30 mM | 0.0126 mL | 0.0632 mL | 0.1265 mL | 0.3162 mL |


PSMα3 Related Classifications
HY-P2358 Related Classifications
 Powered by Bioz