



Rifaximin-d6
Based on 1 Customer Validation
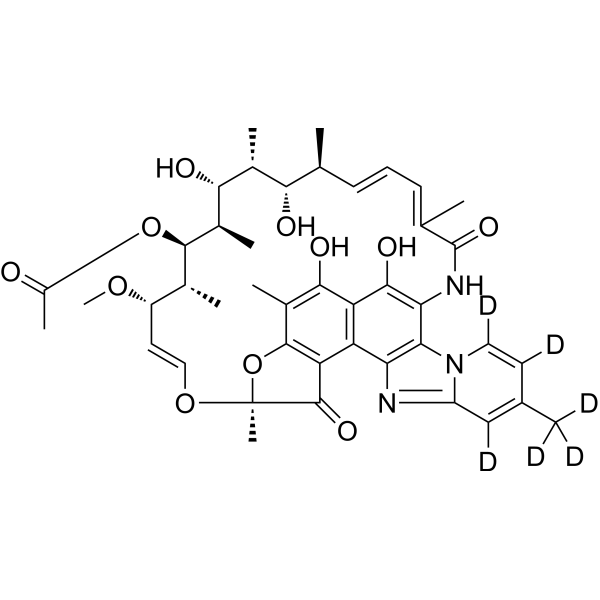
Rifaximin-d6 is the deuterium labeled Rifaximin. Rifaximin is an orally administered, semi-synthetic, nonsystemic antibiotic derived from rifamycin SV with antibacterial activity.
For research use only. We do not sell to patients.
- CAS No.: 1262992-43-7
- Formula: C43H45D6N3O11
- Molecular Weight:791.92
-
Storage:Powder -20°C, 3 years ; In solvent -80°C, 6 months , -20°C, 1 month

To place orders, for customer services and technical support, please contact: MedChemExpress USA
Tel: 609-228-6898 E-mail: [email protected] [email protected]


-
 Biological Activity
-
Chemical Information
- Protocols
- Purity & Documentation
- References
-
 Help & FAQs


-
HY-16908
LefamulinAntibiotic -

HY-101274A
(3α,5β,6β,7α)-BAR501Cholane Scaffolds -
HY-122139
Desethylene Ciprofloxacin hydrochlorideDrug Metabolite -
HY-B0075S
Melatonin-d4Stable Isotope -

HY-122139R
Desethylene Ciprofloxacin hydrochloride (Standard)Reference Standard -
HY-B0011S
Docetaxel-d9Stable Isotope
All Antibiotic Isoforms
More

Biological Activity
Description
In Vitro
Stable heavy isotopes of hydrogen, carbon, and other elements have been incorporated into drug molecules, largely as tracers for quantitation during the drug development process. Deuteration has gained attention because of its potential to affect the pharmacokinetic and metabolic profiles of drugs[1].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only. Further protocols information, click here.
Application
1. This compound can be used as a tracer
2. This compound can be used as an internal standard for quantitative analysis by NMR, GC-MS, or LC-MS.


Chemical Information
-
CAS No. 1262992-43-7
-
Unlabeled CAS 80621-81-4
-
Appearance Solid
-
Molecular Weight 791.92
-
Formula C43H45D6N3O11
-
Color Yellow to orange
-
SMILES
O=C1C2=C(O[C@@]1(O/C=C/[C@@H]([C@H]([C@H]([C@@H]([C@@H]([C@@H]([C@@H](O)[C@@H](C)/C=C/C=C(C)\C3=O)C)O)C)OC(C)=O)C)OC)C)C(C)=C(O)C4=C2C5=C(C(N3)=C4O)N6C(C([2H])=C(C([2H])([2H])[2H])C([2H])=C6[2H])=N5
-
Shipping
Room temperature in continental US; may vary elsewhere.
-
Storage
Powder -20°C 3 years In solvent -80°C 6 months -20°C 1 month

Protocols
-
Research Protocol for Infectious Diseases
Infectious-disease experiments test how pathogens interact with host barriers, innate immune receptors, inflammatory signaling, pathogen replication, and tissue injury; pattern-recognition receptors such as TLRs, RIG-I-like receptors, NOD-like receptors, and inflammasomes detect microbial molecules and activate NF-κB, interferon, and cytokine responses. The central hypothesis is that infection severity reflects the balance between pathogen burden and host response: protective inflammation restricts pathogen growth, whereas excessive or mislocalized inflammation contributes to tissue damage and disease phenotype. Unresolved questions include which host pathways are protective versus pathogenic, why some infection models fail to translate to human disease, and which combined readouts best predict clinically relevant infection outcomes.
-
Bacterial live/dead nucleic-acid viability staining
The LIVE/DEAD bacterial viability staining method is based on differential permeability of nucleic-acid-binding fluorescent dyes, most commonly SYTO 9 and propidium iodide (PI), which enables discrimination of bacterial populations with intact versus compromised cytoplasmic membranes. SYTO 9 penetrates both intact and damaged bacterial membranes and binds nucleic acids to produce green fluorescence, whereas propidium iodide penetrates only cells with compromised membranes and fluoresces red while also reducing SYTO 9 signal through competitive binding and fluorescence interactions. The resulting fluorescence pattern is interpreted as a proxy for membrane integrity, which is widely used as an indicator of bacterial viability in microscopy, flow cytometry, and spectroscopic platforms. However, mechanistic studies show that SYTO 9 and PI interactions involve displacement and fluorescence resonance energy transfer effects, which can influence signal interpretation depending on dye ratios a


Purity & Documentation
-
Data Sheet (274 KB)
-
SDS (252 KB)
- English - EN (252 KB)
- Français - FR (252 KB)
- Deutsch - DE (252 KB)
- Norwegian - NO (252 KB)
- Español - ES (252 KB)
- Swedish - SV (252 KB)
- Italian - IT (252 KB)
- Korean - KR (252 KB)
- Portuguese - PT (252 KB)
-
Handling Instructions (2659 KB)
References
[1]. Russak EM, et al. Impact of Deuterium Substitution on the Pharmacokinetics of Pharmaceuticals. Ann Pharmacother. 2019;53(2):211-216. [Content Brief]
[2]. Cruciani F, Brigidi P, Calanni F et al. Efficacy of rifaximin vaginal tablets in treatment of bacterial vaginosis: a molecular characterization of the vaginal microbiota. Antimicrob Agents Chemother. 2012 Aug;56(8):4062-70. [Content Brief]
[3]. Cremonini F, Lembo A. Rifaximin for the treatment of irritable bowel syndrome. Expert Opin Pharmacother. 2012 Feb;13(3):433-40. [Content Brief]
[4]. Rivkin A, Gim S. Rifaximin: new therapeutic indication and future directions. Clin Ther. 2011 Jul;33(7):812-27. [Content Brief]
[5]. Cottreau J, Baker SF, DuPont HL, Garey KW. Rifaximin: a nonsystemic rifamycin antibiotic for gastrointestinal infections. Expert Rev Anti Infect Ther. 2010 Jul;8(7):747-60. [Content Brief]
[6]. Koo HL, DuPont HL. Rifaximin: a unique gastrointestinal-selective antibiotic for enteric diseases. Curr Opin Gastroenterol. 2010 Jan;26(1):17-25. [Content Brief]
[7]. Ojetti V, Lauritano EC, Barbaro F et al. Rifaximin pharmacology and clinical implications. Expert Opin Drug Metab Toxicol. 2009 Jun;5(6):675-82. [Content Brief]

Calculators
Concentration (start) × Volume (start) = Concentration (final) × Volume (final)


Rifaximin-d6 Related Classifications
HY-13234S Related Classifications
 Powered by Bioz