



Patiromer

Based on 1 Customer Validation
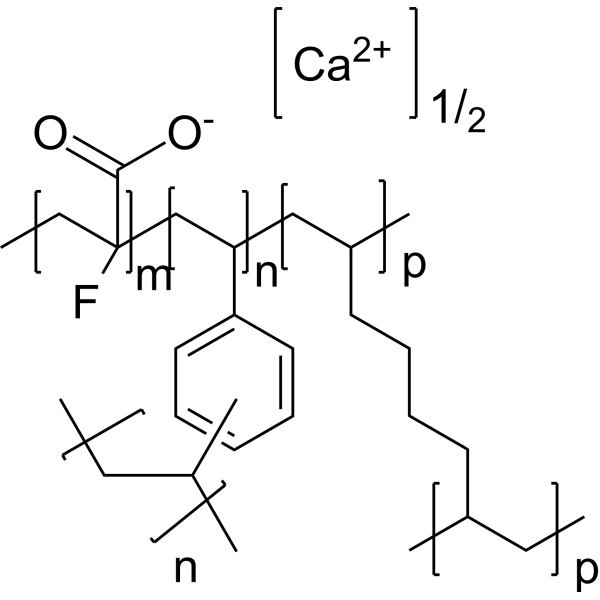
Patiromer is an orally active, selective and non-absorbable intestinal potassium (K+) polymer binder that reversibly binds potassium ions in exchange for calcium (Ca2+). Patiromer can rapidly and continuously reduce serum potassium levels, maintain a normal blood potassium state, and reduce serum aldosterone levels. Patiromer also increases fecal potassium excretion. Patiromer is mainly used in the study of hyperkalemia associated with diseases such as chronic kidney disease, diabetes, and heart failure, and is particularly suitable for improving renin-angiotensin-aldosterone system inhibitor (RAASi) therapy.
Nur für Forschungszwecke. Wir verkaufen nicht an Patienten.
- Reinheit : 95.0%
- CAS. Nr.: 1208912-84-8
- Formel: C28H48CaFO2+
-
Speicherung:
Please store the product under the recommended conditions in the Certificate of Analysis.

To place orders, for customer services and technical support, please contact: MedChemExpress USA
Tel: 609-228-6898 E-mail: [email protected] [email protected]


-
 Biologische Aktivität
-
Chemical Information
-
Lösungsmittel & Löslichkeit
- Protokoll
- Reinheit & Dokumentation
- Verweise
-
 Help & FAQs




Biologische Aktivität
Beschreibung
IC50 & Target
|
JAK3 33.1 nM (IC50) |
IL-2 |
IL-4 |
IL7R |
IL-15 |
STAT3 |
STAT5 |
STAT6 |
In Vitro
Patiromer is a sodium-free, non-absorbable K+ binding polymer[2].
Patiromer has a significantly higher potassium binding capacity in vitro than traditional resins such as polystyrene sulfonate and has high-capacity potassium binding properties[3].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only. Further protocols information, click here.
In Vivo
Animal Dosing Preparation:
This product is orally active and is routinely administered via gavage or feed. For gavage administration, due to its poor water solubility, prepare the dosage based on the daily powder requirement and volume for each animal before administration. The specific procedure is as follows:
Weigh the appropriate amount of powder and add an appropriate amount of drinking water. Vortex or stir thoroughly. The powder will not completely dissolve at this point; the system will be a homogeneous suspension. Administer the solution via gavage immediately after preparation. If powder residue remains in the container after administration, add a small amount of pure water, stir well, and administer via gavage again immediately. Repeat this step if necessary to ensure the animal ingests all the powder.
Precautions:
1. The gavage volume must be strictly controlled within a reasonable range. For rats and mice, it is recommended not to exceed 10 mL/kg.
2. This product is poorly soluble in water; the suspension should be used immediately after preparation and should not be stored for extended periods.
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only.
-
Animal Model:Spontaneously hypertensive rats (SHR) (male, 200-250 g, 7-9 weeks old) with unilateral nephrectomy (UniNx)[2]
-
Dosage:4 g/kg
-
Administration:Oral gavage, once daily, 8 days; rats were induced chronic hyperkalemia by 3% potassium diet and amiloride.
-
Result:Significantly reduced serum K+ from baseline at days 4 and 8, and serum aldosterone was reduced to baseline levels, with no significant clinical distress in animals.
Clinical Trial
| NCT Number | Sponsor | Condition | Start Date |
Phase

|
|---|---|---|---|---|
| NCT01329991 | Plexxikon| | 2011-05 | PHASE1 |


Chemical Information
-
CAS. Nr. 1208912-84-8
-
Appearance Solid
-
Formel C28H48CaFO2+
-
Color White to light yellow
-
SMILES
CCC(C([O-])=O)(F)CC(C1=CC=CC=C1)CC(CCCCC(C)CC)C.CC(CC)C.[Ca+2].[p].[p].[n].[m].[n].[1/2]
-
Versand
Room temperature in continental US; may vary elsewhere.
-
Speicherung
Please store the product under the recommended conditions in the Certificate of Analysis.


Lösungsmittel & Löslichkeit
In Vitro:
H2O : < 0.1 mg/mL (insoluble)

Protokoll
-
Research Protocol for Cardiovascular Diseases
Cardiovascular disease can be modeled as maladaptive cardiac remodeling, where ischemic injury or pressure overload activates inflammatory signaling, fibroblast activation, extracellular-matrix deposition, cardiomyocyte hypertrophy, vascular remodeling, and progressive ventricular dysfunction. The TGF-β/SMAD axis is a central profibrotic pathway after myocardial injury and pressure overload, while innate immune and cytokine pathways regulate leukocyte recruitment, scar formation, and adverse remodeling. Key unresolved questions include which inflammatory signals are reparative versus harmful, when fibrosis is protective versus maladaptive, and whether pathway inhibition improves function without weakening necessary infarct healing or compensatory remodeling.
-
Ca2+ Staining Technique
Ca2+ staining is an experimental technique that utilizes specific fluorescent probes (such as Fluo-4 AM, Fura-2, etc.) to qualitatively or quantitatively detect dynamic changes in intracellular Ca2+ concentrations; this is achieved by monitoring the changes in fluorescent signals generated when these probes bind to free intracellular calcium ions. The underlying principle relies primarily on the presence of chelating groups within the probe's molecular structure that possess high affinity for calcium ions.
-
Research Protocol for Metabolic Diseases
AMP-activated protein kinase, AMPK, is a conserved cellular energy sensor that responds to reduced cellular energy status and coordinates metabolism by increasing ATP-generating catabolic pathways while suppressing ATP-consuming anabolic processes. In metabolic disease research, the AMPK pathway is experimentally relevant because it regulates hepatic lipid synthesis, fatty acid oxidation, glucose production, skeletal-muscle glucose disposal, mTORC1-linked biosynthesis, autophagy, mitochondrial homeostasis, and whole-body energy balance. The central pathway logic is that energy stress, metformin, exercise-like stimulation, or direct AMPK activators increase AMPKα Thr172 phosphorylation and downstream substrate phosphorylation, including ACC and RAPTOR. Phosphorylation of ACC suppresses lipogenesis and supports fatty acid oxidation, whereas phosphorylation of RAPTOR suppresses mTORC1 signaling and links cellular energy status to growth and protein synthesis control. The pathway is linked


Reinheit & Dokumentation
-
Data Sheet (281 KB)
-
SDS (251 KB)
- English - EN (251 KB)
- Français - FR (251 KB)
- Deutsch - DE (251 KB)
- Norwegian - NO (251 KB)
- Español - ES (251 KB)
- Swedish - SV (251 KB)
- Italian - IT (251 KB)
- Korean - KR (251 KB)
- Portuguese - PT (251 KB)
-
Handling Instructions (2659 KB)
Verweise
[1]. Weir MR, et al. Patiromer in patients with kidney disease and hyperkalemia receiving RAAS inhibitors. N Engl J Med. 2015 Jan 15;372(3):211-21. [Content Brief]
[2]. Iyer SPN, et al. Pharmacodynamic effects of the K+ binder patiromer in a novel chronic hyperkalemia model in spontaneously hypertensive rats. Physiol Rep. 2020 Sep;8(18):e14572. [Content Brief]
[3]. Colbert GB, et al. Patiromer for the treatment of hyperkalemia. Expert Rev Clin Pharmacol. 2020 Jun;13(6):563-570. [Content Brief]

Calculators
Konzentration (Stammlösung) × Volumen (Stammlösung) = Konzentration (Ziellösung) × Volumen (Ziellösung)


Patiromer Related Classifications
HY-112961 Related Classifications
 Powered by Bioz