



Obesity is a chronic, progressive disease that substantially increases the risk of multiple comorbidities, including type 2 diabetes (T2D), cardiovascular diseases, and nonalcoholic fatty liver disease (NAFLD), ultimately impairing quality of life. In recent years, GLP-1 receptor agonists (GLP-1RAs) have emerged as cornerstone therapies for obesity and T2D by regulating insulin and glucagon secretion, suppressing appetite, and delaying gastric emptying, with Tirzepatide—the first approved dual GLP-1/GIP receptor agonist—serving as a leading example of their remarkable weight-loss efficacy and metabolic benefits. Alongside these developments, triple incretin agonists are currently under clinical investigation, driving the advancement of therapeutic mechanisms; oral GLP-1RA formulations are in development to improve treatment convenience; and the emergence of multiple novel targets is paving the way for innovative directions in next-generation obesity research.
In this article, we explore next-generation obesity therapies from three perspectives: GLP-1-based multi-receptor agonists, oral GLP-1 strategies, and novel obesity targets such as the amylin receptor (AMYR), GPR75 and activin type II receptors (ActRII). Together, these discussions aim to provide insights into future obesity drug discovery and translational research.
- GLP-1-based Multi-Receptor Agonists: Synergistic Metabolic Regulation
- Oral GLP-1 Solution: Convenient and Patient-Friendly
- Emerging Targets: Expanding the Landscape of Obesity Therapy
GLP-1 (Glucagon-like peptide-1) is an incretin hormone secreted by intestinal L cells. It activates the GLP-1 receptor (GLP-1R) in a glucose-dependent manner, potentiating insulin release while suppressing glucagon secretion. Beyond its pancreatic effects, GLP-1 acts on the central nervous system to delay gastric emptying and increase satiety, thereby improving glycemic control and promoting weight loss. Early-approved GLP-1RAs, such as liraglutide and semaglutide, have demonstrated robust efficacy and safety for both T2D and obesity.
However, these single-target GLP-1 therapies are limited in their maximal potential for weight loss and metabolic improvements, prompting the development of multi-receptor agonists. By simultaneously activating GLP-1R along with other relevant receptors, such as glucose-dependent insulinotropic polypeptide receptor (GIPR) and glucagon receptor (GCGR), multi-receptor agonists exert synergistic effects on glucose homeostasis, appetite regulation, lipid metabolism, and energy expenditure, resulting in enhanced weight-loss efficacy.
| Drugs |
Developer | Mechanism of action |
Clinical development (Phase / NCT) |
|---|---|---|---|
| Tirzepatide | Eli Lilly (Indianapolis, IN, USA) | GLP-1R/GIPR | Approved |
| VK2735 | Viking Therapeutics, Inc. (San Diego, CA, USA) | GLP-1R/GIPR | Phase III (NCT07104500) |
| CT-388 | Roche (Basel, Switzerland) / Carmot Therapeutics (Berkeley, CA, USA) | GLP-1R/GIPR | Phase II (NCT06628362) |
| AMG133 | Amgen (Thousand Oaks, CA, USA) | GLP-1R/GIPR | Phase III (NCT06858878) |
| Survodutide | Boehringer Ingelheim (Basel, Switzerland) | GLP-1R/GCGR | Phase III (NCT06066528) |
| Pemvidutide | Altimmune (Gaithersburg, MD, USA) | GLP-1R/GCGR | Phase II (NCT05989711) |
| Efinopegdutide | Merck (Kenilworth, NJ, USA) / Hanmi Pharmaceutical (Seoul, South Korea) | GLP-1R/GCGR | Phase II (NCT05877547) |
| Amycretin | Novo Nordisk (Bagsværd, Denmark) | GLP-1R/AMYR | Phase II (NCT06064006) |
| Dapiglutide | Zealand Pharma (Copenhagen, Denmark) | GLP-1R/GLP-2R | Phase II (NCT05788601) |
| Retatrutide | Eli Lilly (Indianapolis, IN, USA) | GLP-1R/GIPR/GCGR | Phase III (NCT05931367) |
| HM15275 | Hanmi Pharmaceutical (Seoul, South Korea) | GLP-1R/GIPR/GCGR | Phase II (NCT07205900) |
Tirzepatide is a long-acting GLP-1R/GIPR dual agonist approved by the FDA for T2D and obesity.
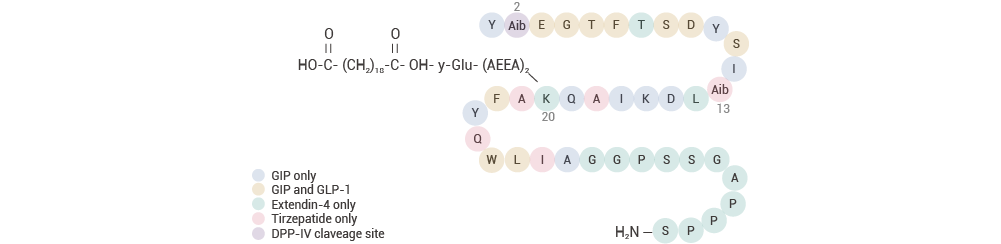
Figure 1. Structure of Tirzepatide[1].
It is a 39-mer peptide designed from GLP-1, GIP, and exenatide segments. Substitution with Aib at positions 2 and 13 confers resistance to DPP-4 and enhances stability. Additionally, a C20 fatty di-acid moiety is attached to Lys-20 to enable albumin binding, extending its half-life to five days (Figure 1)[1].
Tirzepatide has demonstrated unprecedented efficacy in weight reduction and metabolic benefits, and it is also being investigated for NASH and CKD, highlighting the therapeutic potential of a multi-target strategy.

Figure 2. Retatrutide exerts functions via combinatorial agonism[2].
Retatrutide is a leading multi-receptor agonist candidate in phase III trials, activating GLP-1R, GIPR, and GCGR. Its triple-receptor profile enables appetite suppression and insulin secretion (via GLP-1R), enhanced glucose-dependent insulin release and lipid metabolism (via GIPR), and increased energy expenditure with hepatic metabolic regulation (via GCGR)[2]. Innovative molecular design improves stability, bioavailability, and half-life, resulting in superior weight-loss and metabolic outcomes.
Collectively, multi-receptor GLP-1 agonists represent a major trend in next-generation therapies by integrating weight loss, glycemic control, and metabolic improvement into a single pharmacological strategy. Formulation advances are now extending these benefits to oral GLP-1RAs, broadening the range of therapeutic options.
Approved GLP-1RA agents are primarily peptide-based and administered via injection, which can negatively affect patient compliance and limit therapeutic efficacy. Substantial efforts are focused on developing oral GLP-1RAs to improve convenience and adherence. Current approaches fall into two main categories.
Absorption enhancers are commonly used in oral peptide formulations to overcome enzymatic degradation and poor gastrointestinal permeability.
For example, SNAC (Sodium N‑[8-(2-hydroxybenzoyl)amino]caprylate) is employed in oral semaglutide formulations. SNAC increases local gastric pH, stabilizing semaglutide against proteolytic degradation and enhancing transcellular absorption across the gastric epithelium. Clinical investigations show that daily administration of this formulation over 68 weeks can achieve 15.1% body weight reduction in 50 mg dosing group[3], providing an effective alternative for patients who prefer non-injectable treatments.
Developing small-molecule therapeutics is a well-established strategy for enabling oral administration. Currently, multiple small-molecule GLP-1RAs have been designed and advanced into clinical evaluation. Representative examples include danuglipron, orforglipron, Boc5, and TT-OAD2. Many of these compounds exhibit G protein–biased signaling, preferentially activating the cAMP pathway while reducing β-arrestin recruitment, which may help limit receptor desensitization and associated adverse effects.
| Agonist |
Developer | Mechanism / Binding profile | Clinical development (Phase / NCT) |
|---|---|---|---|
| Boc5 | Institute of Materia Medica (Shanghai, China) | Orthosteric full agonist; Biased signaling profile with no β-arrestin recruitment; Orthosteric partial agonist | - |
| TT-OAD2 | Eli Lilly (Indianapolis, IN, USA) | Biased signaling profile with no β-arrestin recruitment | - |
| TTP-273 | vTv Therapeutics (High Point, NC, USA) | Orthosteric partial agonist; Biased signaling profile | Phase IIa (NCT02653599) |
| Danuglipron (PF-06882961) | Pfizer (New York, NY, USA) | Orthosteric full agonist for cAMP signaling; Partial activation of other pathways | Phase IIb (NCT04707313) |
| Orforglipron (LY3502970, OWL833) | Eli Lilly (Indianapolis, IN, USA) / Chugai Pharmaceutical (Tokyo, Japan) | Orthosteric partial agonist; Biased signaling profile with no β-arrestin recruitment | Phase III (NCT05869903) |
| HRS-7535 | Shandong Suncadia Medicine (Lianyungang, Jiangsu, China) / Kailera Therapeutics (San Diego, CA, USA) |
ND | Phase II (NCT06250946) |
| ECC5004 (AZD5004) | Eccogene (Shanghai, China) / AstraZeneca (Cambridge, UK) | Orthosteric full agonist; Biased signaling profile with no β-arrestin recruitment | Phase IIb (NCT06579105) |
| CT-996 | Roche (Basel, Switzerland) / Carmot herapeutics (Berkeley, CA, USA) | Orthosteric partial agonist; Biased signaling profile with reduced β-arrestin recruitment | Phase II (NCT07112872) |
| Aleniglipron (GSBR-1290) | Structure Therapeutics (Shanghai, China) / Gasherbrum Bio / (San Francisco, CA, USA)Orthosteric full agonist; Biased signaling |
Orthosteric full agonist; Biased signaling profile with no β-arrestin recruitment | Phase IIb (NCT06693843) |
| ID110521156 | Yunovia (Gyeonggi-do, Republic of Korea) / Ildong Pharmaceutical (Seoul, Republic of Korea) | Orthosteric full agonist; Partial / no activation of other pathways | Phase I (NCT06635226) |

Figure 3. Structure of Orforglipron.
Orforglipron (LY3502970) is a highly selective oral GLP-1RA with optimized pharmacokinetic properties. Clinical trials indicate that daily dosing of 36 mg orforglipron reduced body weight by 9.6% in patients with T2D and 11.3% in patients with obesity without diabetes over 72 weeks, along with a favorable safety profile[5-6]. Orforglipron's non-peptide structure supports long-term use and high patient compliance.

Figure 4. Structure of danuglipron.
Danuglipron (PF-06882961) is another small-molecule GLP-1RA developed by Pfizer. This agent selectively activates cAMP pathway while exhibiting low β-arrestin recruitment, thereby reducing the risk of receptor desensitization. Preclinical models demonstrate significant reductions in food intake and body weight, alongside improvements in glucose and lipid metabolism[7]. A Phase II trial showed that daily oral dosing of danuglipron reduced HbA1c by approximately 1.04–1.57% and produced 1.93–5.38 kg of weight loss over 12 weeks, with statistical significance[8].
The development of oral GLP-1RA highlights the feasibility of convenient and effective therapies for the long-term management of obesity and metabolic diseases. With continued advances in formulation optimization and long-term clinical validation, these agents are poised to become a next-generation, patient-friendly GLP-1RA therapy. Beyond GLP-1-based therapies, researchers are increasingly investigating novel molecular targets to complement these approaches.
GLP‑1 and GLP-1-based multi-target therapies have achieved impressive efficacy in promoting weight loss and improving metabolic outcomes. Nevertheless, challenges remain, including incomplete fat reduction, difficulty in preserving lean mass, and considerations for long-term adherence. These ongoing unmet needs have spurred interest in novel therapeutic targets and integrated strategies designed to further optimize metabolic health. Key targets that are currently being investigated to complement GLP-1-based approaches include AMYR, melanocortin receptor 4 (MC4R), GPR75, ActRII, and other emerging molecules, which are discussed in detail below:

Figure 5. Structure of human amylin.
Amylin is a 37–amino acid peptide hormone co-secreted with insulin by pancreatic β cells. It regulates food intake, gastric motility, glucose homeostasis, and energy metabolism by activating distinct AMYR subtypes (1-3), each of which is composed of the calcitonin receptor (CTR) in complex with one of three corresponding receptor activity-modifying proteins (RAMPs)[9-10]. Amylin-based agents may offer improved muscle preservation and enhanced gastrointestinal tolerability, act synergistically with GLP-1RAs, and exert favorable effects on body weight regulation and metabolic flexibility[9-10].
Recent clinical breakthroughs with amylin-based strategies have sparked a surge of research activity. Typically, Roche's petrelintide achieved 8.3% weight loss over 16 weeks[11], and Eli Lilly's eloralintide produced 11.3% weight loss over 12 weeks as a monotherapy[12]. Moreover, CagriSema (a combination of cagrilintide and semaglutide) achieved 15.6% weight loss over 32 weeks[13], and oral amycretin, a dual GLP-1R/AMYR agonist, set a new record with 13.1% weight loss over 12 weeks[14]. These results emphasize that AMYR represents a promising solution for weight management.
The MC4R belongs to the melanocortin receptor family of GPCRs, which also includes MC1R, MC2R, MC3R, and MC5R. MC4R is predominantly expressed in the central nervous system and plays a critical role in controlling appetite and feeding behavior.
MC4R-associated signaling pathways include leptin–melanocortin pathway, G protein–mediated signaling, β-arrestin signaling, and Ca²⁺-dependent pathways, all of which are closely linked to obesity and energy metabolism. The association between MC4R and obesity is well established, with disease-causing mutations affecting 1% to 6% of obese patients[15]. Moreover, two therapies are already approved—setmelanotide for obesity and bremelanotide for hypoactive sexual desire disorder—while several candidates such as PL7737 and bivamelagon are under clinical investigation, demonstrating the feasibility of MC4R as a target for anti-obesity drug discovery.
GPR75 is an orphan G protein–coupled receptor (GPCR) and is most abundantly expressed in the brain, with additional expression detected in the heart, kidney, and prostate. GPR75 was first identified by Tarttelin et al. in 1999[16]. Interest in GPR75 as a novel obesity target originated from a landmark study published by Regeneron in Science in 2021[17]. Sequencing of 640,000 exomes identified GPR75 variants associated with decreased obesity risk. Preclinical knockout models further confirmed that GPR75 knockout led to reductions in body weight, blood glucose, and insulin levels[17]. Following this finding, Regeneron and AstraZeneca initiated a collaboration aimed at developing small-molecule GPR75 modulators for the treatment of obesity and its associated comorbidities.
ActRII, including ActRIIA and ActRIIB, belong to the TGF-β receptor family and are involved in a broad range of physiological processes. Unlike many existing weight-loss therapies, which are often associated with loss of lean mass, targeting ActRII has the potential to promote fat reduction while increasing muscle mass, thereby mitigating the risk of frailty, particularly in elderly populations[18].
Currently, there are two approved ActRII-based protein therapeutics—Sotatercept and Luspatercept—but not for obesity. ActRII candidates in development for weight management are mainly antibody-based, such as Bimagrumab, LAE102 and LAE123. Biotech companies like Supercede Therapeutics are developing oral small-molecule inhibitors targeting ActRII, exploring the potential of ActRII signaling blockade for weight management.
In addition to the aforementioned popular targets, recent research has explored other potential obesity targets. For example, INHBE (Inhibin Beta E)-targeted oligonucleotide therapies such as WVE-007 are being investigated for promoting fat loss while preserving muscle mass, and fibroblast growth factor 21 (FGF-21) and growth differentiation factor 15 (GDF-15) are being evaluated for their roles in regulating appetite and energy metabolism.
These emerging targets not only provide complementary mechanisms for single-target therapies but also lay the foundation for multi-target combination strategies, enabling future obesity treatments to achieve weight reduction, muscle preservation, and metabolic optimization simultaneously. Collectively, they highlight a shift from single-target weight loss toward comprehensive metabolic management, opening innovative avenues for next-generation therapies that are safer, more effective, and better tolerated.
Great success of GLP-1–based therapies has catalyzed a paradigm shift in obesity treatment. Drug development is moving beyond single-target approaches and injectable peptides toward multi-target strategies, oral formulations, and comprehensive metabolic management. This evolution is exemplified by multi-receptor GLP-1 agonists, which enhance weight loss and metabolic regulation through synergistic activation of GLP-1R, GIPR, and GCGR; oral GLP-1 therapies, which improve patient convenience and long-term adherence; and emerging targets such as AMYR, GPR75, MC4R, and ActRII, which offer novel mechanisms to promote fat loss, preserve lean mass, and optimize metabolic health. Together, these advances are shaping a new generation of safer, more effective, and better-tolerated obesity therapies.
 LinkedIn
 Researchgate
 Instagram
 X
 Facebook
 WhatsApp
 Reddit
 Mail
- [1]. Lisco G, et al. Front Endocrinol (Lausanne). 2022 Sep 8;13:920541. [Content Brief]
- [2]. Li W, et al. Cell Discov. 2024 Jul 17;10(1):77. [Content Brief]
- [3]. Knop FK, et al. Lancet. 2023 Aug 26;402(10403):705-719. [Content Brief]
- [4]. Șeremet OC, et al. Medicina (Kaunas). 2025 Oct 23;61(11):1902. [Content Brief]
- [5]. Wharton S, et al. N Engl J Med. 2025 Nov 6;393(18):1796-1806. [Content Brief]
- [6]. Horn DB, et al. Lancet. 2026 Dec 20;406(10522):2927-2944. [Content Brief]
- [7]. Griffith DA, et al. J Med Chem. 2022 Jun 23;65(12):8208-8226. [Content Brief]
- [8]. Buckeridge C, et al. Diabetes Obes Metab. 2025 Sep;27(9):4915-4926. [Content Brief]
- [9]. Rejili M, et al. Vascul Pharmacol. 2025 Dec 2;162:107563. [Content Brief]
- [10]. Walker CS, et al. Nat Rev Endocrinol. 2025 Aug;21(8):482-494. [Content Brief]
- [11]. Hesse D, et al. Diabetes. 2025 Jun 20;74(Suppl 1):1773-P.
- [12]. Bhattachar SN, et al. Diabetes. 2025 Jun 20;74(Suppl 1):882-P.
- [13]. Mikhail N, Wali S. Clin Trials Clin Res. 2023;2(5):2.
- [14]. Kuhre RE, et al. EBioMedicine. 2025 Aug;118:105862. [Content Brief]
- [15]. Fatima MT, et al. Diabetes Obes Metab. 2022 Apr;24(4):583-598. [Content Brief]
- [16]. Tarttelin EE, et al. Biochem Biophys Res Commun. 1999 Jun 24;260(1):174-80. [Content Brief]
- [17]. Akbari P, et al. Science. 2021 Jul 2;373(6550):eabf8683. [Content Brief]
- [18]. Nunn E, et al. Mol Metab. 2024 Feb;80:101880. [Content Brief]

