



BI-1622

Based on 1 Customer Validation
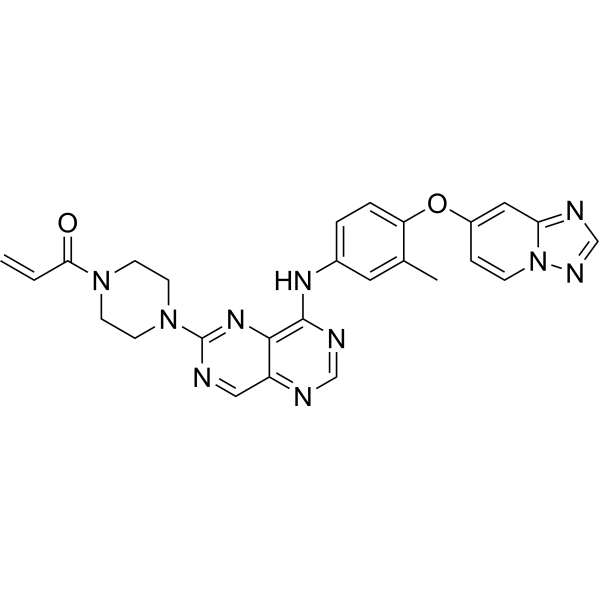
BI-1622 is an orally active, potent and highly selective HER2 (ERBB2) inhibitor, with an IC50 of 7 nM. BI-1622 shows greater than 25-fold selectivity over EGFR. BI-1622 shows high antitumor efficacy in vivo in xenograft mouse tumor models with engineered H2170 and PC9 cells and had a favorable agent metabolism and pharmacokinetics profile.
For research use only. We do not sell to patients.
- Purity : 98.02%
- CAS No.: 2681392-19-6
- Formula: C26H24N10O2
- Molecular Weight:508.53
-
Storage:
4°C, protect from light
* In solvent : -80°C, 6 months; -20°C, 1 month (protect from light)

To place orders, for customer services and technical support, please contact: MedChemExpress USA
Tel: 609-228-6898 E-mail: [email protected] [email protected]


-
 Biological Activity
-
Chemical Information
-
Solvent & Solubility
- Protocols
- Purity & Documentation
- References
-
 Help & FAQs

All EGFR Isoforms
More

Biological Activity
Description
IC50 & Target
|
HER2 7 nM (IC50) |
ErbB4 |
EGFR |
CDK11B |
JAK3 |
In Vitro
BI-1622 (0-5 µM, 72 h or 96 h) inhibits the proliferation of HER2-dependent cell lines[1].
BI-1622 induces a dose-dependent decrease in pHER2 and pERK levels in NCI-H2170 HER2YVMA and PC-9 HER2YVMA cells with an accompanying decrease in DUSP6 messenger RNA levels[1].
BI-1622 displays good permeability and no PgP-mediated efflux liability[1].
BI-1622 shows good in vitro clearance in mouse liver microsomes and mouse hepatocytes[1].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only. Further protocols information, click here.
-
Cell Line:Ba/F3 cells
-
Concentration:0-5 µM
-
Incubation Time:72 h or 96 h
-
Result:Potently inhibited the proliferation of cancer cell lines dependent on amplified HER2 or an NRG-1 fusion. Inhibited different HER2 oncogenic variants and HER2WT with IC50 values below 50 nM in tumor cell lines, while sparing EGFRWT-driven cells.
In Vivo
BI-1622 (0-100 mg/kg, orally, twice daily) inhibits tumor growth and inhibits oncogenic signaling in vivo[1].
MedChemExpress (MCE) has not independently confirmed the accuracy of these methods. They are for reference only.
-
Animal Model:Female NMRI-Foxn1nu mice (6-8 weeks old, 8-10 mice per cage, engrafted subcutaneously with PC-9 HER2YVMA, NCI-H2170 HER2YVMA or NCI-N87 cells)[1]
-
Dosage:10, 30 and 100 mg/kg
-
Administration:orally, twice daily
-
Result:In the NCI-H2170 HER2YVMA mechanistic model, 100 mg/kg twice daily BI-1622 resulted in a delay in tumor growth (73% TGI). In the ST3107 HER2 exon 20 mutant model, both BI-4142 (100 mg/kg twice daily) resulted in tumor regressions.
-
Animal Model:NMRI Foxn1nu mice (n=3 per group)[1]
-
Dosage:1 mg/kg (IV); 10 and 100 mg/kg (Orally)
-
Administration:IV, Orally; once (Pharmacokinetic Analysis)
-
Result:Showed moderate in vivo clearance (50% hepatic blood flow), a moderate volume of distribution, and good to moderate bioavailability of up to 68%.


Chemical Information
-
CAS No. 2681392-19-6
-
Appearance Solid
-
Molecular Weight 508.53
-
Formula C26H24N10O2
-
Color Light yellow to yellow
-
SMILES
O=C(N1CCN(CC1)C2=NC3=C(NC4=CC=C(C(C)=C4)OC5=CC6=NC=NN6C=C5)N=CN=C3C=N2)C=C
-
Shipping
Room temperature in continental US; may vary elsewhere.
-
Storage
4°C, protect from light
* In solvent : -80°C, 6 months; -20°C, 1 month (protect from light)


Solvent & Solubility
In Vitro:
DMSO : 100 mg/mL (196.65 mM; Need ultrasonic; Hygroscopic DMSO has a significant impact on the solubility of product, please use newly opened DMSO)
Please refer to the solubility information to select the appropriate solvent. Once prepared, please aliquot and store the solution to prevent product inactivation from repeated freeze-thaw cycles.
Storage method and period of stock solution: -80°C, 6 months; -20°C, 1 month (protect from light). When stored at -80°C, please use it within 6 months. When stored at -20°C, please use it within 1 month.
Concentration (start) × Volume (start) = Concentration (final) × Volume (final)

Protocols
-
Patient-Derived Xenograft (PDX)
Patient-derived xenograft (PDX) models are generated by engrafting primary human tumor tissue directly into immunodeficient mice, allowing in vivo propagation of patient tumor biology without initial in vitro adaptation. These models are used to preserve key histopathological and molecular characteristics of the original tumor and enable assessment of tumor growth dynamics and therapeutic response in a living organism. The biological readout is tumor engraftment and subsequent growth in the murine host, which reflects the ability of human tumor cells to survive, vascularize, and expand in an immunocompromised microenvironment.
-
Protocol for Pharmacokinetic Study
Pharmacokinetic studies quantify how an organism handles a drug over time through absorption, distribution, metabolism, and excretion, and the core experimental readout is the concentration-time profile of parent drug and, when relevant, metabolites in biological matrices such as plasma, whole blood, urine, bile, or tissue. Pharmacokinetic analysis links dose, route, exposure, clearance, half-life, distribution, bioavailability, and systemic exposure to drug efficacy and toxicity hypotheses rather than measuring a signaling pathway directly. The literature links pharmacokinetics to drug-development phenotypes by showing that drug metabolism and pharmacokinetics influence compound progression, exposure-response interpretation, safety margins, dosing strategy, and failure risk during discovery and development. DMPK science contributes to compound optimization by integrating physicochemical properties, in vitro metabolism, transporter behavior, in vivo exposure, and pharmacodynamic contex
-
Splenic/Portal-Vein Liver Metastasis Xenograft
Splenic and portal-vein liver metastasis xenograft models deliver tumor cells into the portal circulation so that cells reach the liver first and form hepatic metastatic lesions; splenic injection uses the spleen as an access route to the portal system, while direct portal-vein injection introduces cells into the portal vein without requiring splenectomy. The assay detects liver colonization, intrahepatic tumor growth, tumor distribution, treatment response, survival, and liver-metastasis microenvironment changes; readouts include bioluminescence or fluorescence imaging, gross liver nodule counts, liver weight or tumor burden, histology, and survival.
-
Subcutaneous Cell-Line-Derived Xenograft
Subcutaneous cell-line-derived xenograft (CDX) models are established by implanting cultured human cancer cell lines into immunodeficient mice, where the injected cells form localized tumors that can be monitored in vivo as a measure of tumorigenic potential, growth kinetics, and treatment response. These models are widely used in oncology research because they allow reproducible tumor formation and enable comparative assessment of tumor growth between different cell lines or genetic manipulations in a controlled in vivo microenvironment. Subcutaneous implantation of cancer cells in immunodeficient mice is a standard approach for evaluating tumor growth behavior and therapeutic response across multiple cancer types, including prostate, esophageal, pancreatic, and colon cancer models.
-
Orthotopic Cell-Line Xenograft
Orthotopic cell-line xenograft models involve implantation of human cancer cell lines into the anatomically corresponding organ of immunodeficient mice to reproduce tumor growth within a native microenvironment, enabling more clinically relevant tumor behavior compared with subcutaneous models. These models are widely used because orthotopic placement better recapitulates tumor progression, including invasion and metastatic spread, which are often underrepresented in heterotopic implantation systems. Compared with conventional xenografts, orthotopic implantation is described as more technically complex but provides improved simulation of tumor-microenvironment interactions and metastatic behavior, making it particularly valuable for translational oncology research. Surgical orthotopic implantation approaches have been emphasized as enabling faithful reproduction of clinical cancer features, including metastasis and disease progression patterns that align with the tumor’s organ of origi
-
Intraperitoneal/Peritoneal Dissemination Xenograft
Intraperitoneal (IP) or peritoneal dissemination xenograft models are based on the introduction of human cancer cells into the peritoneal cavity of immunodeficient mice, where they attach to peritoneal surfaces, form multicellular aggregates or spheroids, and progressively generate disseminated tumor nodules that mimic advanced peritoneal metastatic disease. These models are widely used to study ovarian cancer progression, tumor-microenvironment interactions, and intraperitoneal therapeutic responses, often incorporating bioluminescence or fluorescence imaging to longitudinally monitor tumor burden in vivo. The biological principle relies on the capacity of tumor cells such as SKOV3 or related ovarian carcinoma lines to survive in suspension, aggregate within ascites-like fluid, adhere to mesothelial surfaces, and invade peritoneal organs, thereby recapitulating human peritoneal carcinomatosis patterns observed in advanced disease.


Purity & Documentation
-
Data Sheet (273 KB)
-
SDS (252 KB)
- English - EN (252 KB)
- Français - FR (252 KB)
- Deutsch - DE (252 KB)
- Norwegian - NO (252 KB)
- Español - ES (252 KB)
- Swedish - SV (252 KB)
- Italian - IT (252 KB)
- Korean - KR (252 KB)
- Portuguese - PT (252 KB)
-
Handling Instructions (2659 KB)
References


Complete Stock Solution Preparation Table
Please refer to the solubility information to select the appropriate solvent. Once prepared, please aliquot and store the solution to prevent product inactivation from repeated freeze-thaw cycles.
Storage method and period of stock solution: -80°C, 6 months; -20°C, 1 month (protect from light). When stored at -80°C, please use it within 6 months. When stored at -20°C, please use it within 1 month.
| Optional Solvent | Concentration Solvent Mass | 1 mg | 5 mg | 10 mg | 25 mg |
|---|---|---|---|---|---|
| DMSO | 1 mM | 1.9665 mL | 9.8323 mL | 19.6645 mL | 49.1613 mL |
| 5 mM | 0.3933 mL | 1.9665 mL | 3.9329 mL | 9.8323 mL | |
| 10 mM | 0.1966 mL | 0.9832 mL | 1.9665 mL | 4.9161 mL | |
| 15 mM | 0.1311 mL | 0.6555 mL | 1.3110 mL | 3.2774 mL | |
| 20 mM | 0.0983 mL | 0.4916 mL | 0.9832 mL | 2.4581 mL | |
| 25 mM | 0.0787 mL | 0.3933 mL | 0.7866 mL | 1.9665 mL | |
| 30 mM | 0.0655 mL | 0.3277 mL | 0.6555 mL | 1.6387 mL | |
| 40 mM | 0.0492 mL | 0.2458 mL | 0.4916 mL | 1.2290 mL | |
| 50 mM | 0.0393 mL | 0.1966 mL | 0.3933 mL | 0.9832 mL | |
| 60 mM | 0.0328 mL | 0.1639 mL | 0.3277 mL | 0.8194 mL | |
| 80 mM | 0.0246 mL | 0.1229 mL | 0.2458 mL | 0.6145 mL | |
| 100 mM | 0.0197 mL | 0.0983 mL | 0.1966 mL | 0.4916 mL |


BI-1622 Related Classifications
HY-150023 Related Classifications
 Powered by Bioz